India's first psychological laboratory opened in Calcutta in 1915. Within a generation, Indian psychologists were adapting British and American tests for local use in schools, industry, the armed services and clinics, as a historical review of psychological testing in India records.
That century of practice carries one lesson worth holding before you open any questionnaire. A test's usefulness depends less on how clever its questions look and more on local language, culture, norms and validation.
Which means the most accessible test isn't always the most appropriate one. An English questionnaire you can finish on your phone in five minutes is convenient, and it may still tell you very little if nobody checked it with people who speak your language or share your reference points.
This guide is about reading those results. It covers what the main test families measure, how to interpret a score without turning it into a label, and what to do when a result feels heavy. The Indian evidence stays in front throughout.
What a Psychological Assessment Test Can and Cannot Say
A psychological assessment test is a planned set of questions or tasks that turns experiences, skills, or strengths into comparable information. Think of how you read a weather report. It describes conditions over a set period so you can decide whether to carry an umbrella today. It doesn't tell you what the whole year will be like.
Assessments come in different sizes. Some are short self-checks you finish privately in ten minutes. Others are longer evaluations given by a trained clinical psychologist in a structured setting, with an interview, a few carefully chosen tools and a feedback conversation that explains what the numbers mean.
People ask for that structured check for ordinary reasons. The National Mental Health Survey 2015-16 found that 10.6% of adults had a current mental-health condition, while 13.7% had experienced one during their lifetime. Current anxiety disorders were reported at 3.6% and depressive disorders at 0.8%. When workplace stress, broken sleep or a low mood starts crowding out your days, a clear set of questions is often the easiest first step.
Not every tool hunts for trouble. Well-built assessments also map resilience, compassion, belonging and happiness, which helps when you're building something rather than fixing something.
Worth holding onto: assessments are informational, not diagnostic. A result may suggest that therapy, counselling, or a closer look at your well-being could help, but it cannot confirm anxiety, depression, or any other condition on its own.

The confusion usually starts earlier than the score. Different test families answer completely different questions, and mixing them up is the most common mistake people make. The table in the next section sets them side by side, so you can find your question first and look at a number second.
Types of Tests and the Job Each One Does
Five families cover most of what you'll meet online and in a clinic. Each answers a different question, and each has a decision it can't make alone.
| Test type | What it looks at | Typical use | What it cannot do |
|---|---|---|---|
| Brief symptom screeners such as GHQ-12, PHQ-9, GAD-7 | Recent distress, low mood, worry, daily strain | Early self-check or community screening after suitable guidance | Confirm anxiety, depression, or any diagnosis |
| Aptitude and ability tests | Reasoning, learning potential, job-relevant skills | Education, talent search, workplace selection | Judge character, illness, or personal worth |
| Personality and interest inventories | Traits, motives, values, interests | Counselling, career clarity, self-understanding | Freeze a person into a permanent label |
| Cognitive and neuropsychological tests | Memory, attention, thinking speed | Clinical baseline and change over time | Replace a clinical interview |
| Projective and picture-based methods | Themes in stories or perceptions | Specialist clinical assessment | Stand alone as a diagnosis |
Screens come first because that's what you'll meet
A 12-item General Health Questionnaire, the PHQ-9 for low mood, or the GAD-7 for worry all ask about the recent past. India's Directorate General of Health Services training manual for psychologists treats the GHQ-12 as a screening instrument for common mental disorders, including anxiety and depression, and not as a diagnostic test. The same manual sets out who does what: full assessments belong in structured settings with trained clinical psychologists, while selected brief self-administered questionnaires can be used in community contexts only after appropriate training.
Read that as a division of labour. The questionnaire notices a pattern. A trained person decides what the pattern means, and whether something else explains it better.
Aptitude, personality and thinking tests do very different jobs
Aptitude and ability tests look at reasoning, learning potential and job-relevant skills. They drove India's educational talent searches and workplace selection for decades, and they're good at comparing how quickly people solve particular kinds of problems. They say nothing about character, illness or personal worth.
Personality and interest inventories explore traits, motives, values and interests. They're useful in counselling and career clarity, where the goal is language for how you operate. They go wrong the moment someone treats a profile as a fixed identity rather than a snapshot of preferences.
Cognitive and neuropsychological tests examine memory, attention and thinking speed. Clinicians use them to record a baseline and to compare change over time, which is different from judging how capable a person is. These tools don't replace a clinical interview, because a quiet room and a bad night's sleep can shift a score.
Projective and picture-based methods, including Indian adaptations of the Rorschach and the Thematic Apperception Test, belong in specialist hands. They generate themes worth discussing. They don't stand alone as a diagnosis.
A useful test answers the question you actually asked. If a result doesn't help you decide something concrete, it probably wasn't the right tool for your situation.
So pick the row before you pick the score. Worried about exam stress? An intelligence test won't help. Choosing a career path? A depression screen won't answer it, though it might tell you that now isn't the best week to decide.
Screening Tools in Study Work and Community Life
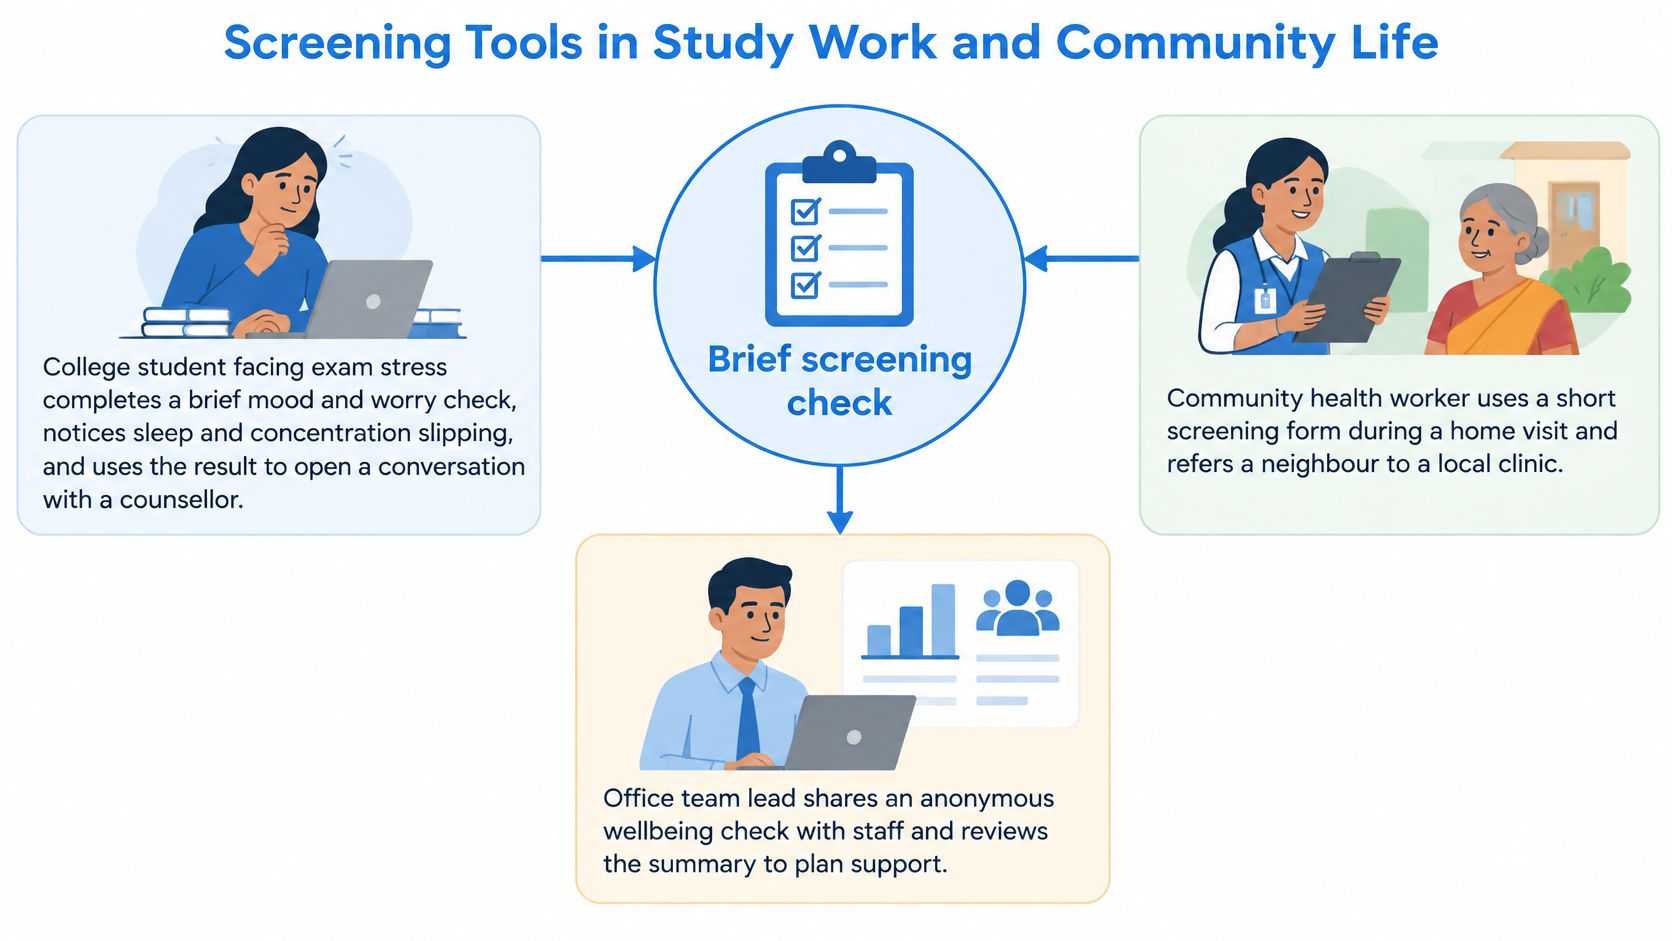
A screen earns its place when it turns a vague worry into a next step. Three everyday situations show the difference.
A college student in exam season fills a short mood and worry check between lectures. The result doesn't surprise her, but seeing it written down makes the pattern real: sleep is slipping, concentration is patchy, and she has snapped at her roommate twice. She books a session with a counsellor and starts rebuilding routines that support her resilience.
A working professional in the middle of burnout takes a stress screen on a Sunday evening. The score confirms what his family already noticed, that workplace stress is following him home and straining his relationships. He uses it to justify rest, to speak to a peer he trusts, and to see a therapist when nothing shifts after a few weeks.
A community health worker visits homes with a short validated checklist. India's National Health Mission operational guidance recommends exactly this pattern: community-level detection with validated checklists, then confirmation at a healthcare facility using established instruments such as the PHQ-9 for depression and AUDIT for alcohol-use disorders. Scale matters here. A 2025 community screening study in Kerala assessed 2,263 residents and found that 9.1% had moderate-or-higher depression.
Where the limits begin
Screening improves case-finding when it's aimed at the right condition. Confirmation still needs a clinical assessment, and that gap is where misreading happens.
A screen works like a smoke alarm. It can warn you that something needs attention, but it cannot say whether the cause is burnt food, a wiring fault, or a kitchen fire. The easiest questionnaire to find is still the wrong one if it was built for a different group or gives no clear next step. The PHQ-9 flags depression symptoms and still needs a clinician to confirm what is going on. AUDIT describes drinking patterns and does not map a full addiction diagnosis. DASS-21 is widely used in research and in digital screens; translation and factor-structure checks alone don't show that a scale works as a screen, so look for evidence of concurrent validity against clinical assessment.
| Instrument | Main focus | Where it is used | Limit to remember |
|---|---|---|---|
| GHQ-12 | Common distress including anxiety and depression | Community screening after training | Not a diagnostic test |
| PHQ-9 | Depression symptoms | Facility-level confirmation in public guidance | Needs a clinical assessment to confirm |
| AUDIT | Alcohol-use patterns | Facility-level confirmation | Does not map a full addiction diagnosis |
| DASS-21 | Depression, anxiety, and stress symptoms | Research and some digital screens | Translation alone does not prove it is a valid screen |
Adolescents, and the case for strengths
Reported mental-health concerns among Indian adolescents range from roughly 4% to 50% depending on the group studied and the method used, as Brookings India's review of school-based adolescent mental health sets out. In the same school-based findings, female students are described as reporting more symptoms of depression and anxiety and lower well-being than male students, with belonging, healthy relationships and resilience-building named as practical supports.
Strengths checks deserve a place beside symptom screens. Asking about compassion, mindfulness and connection often tells a student more about what to protect than a distress score does. A screen that names strain can open the door; a strengths check can show which routines, friendships and supports are worth keeping while that strain is addressed.
Any platform that hosts these questionnaires owes you four details before you start: the instrument version, the Indian-language validation evidence, the group it was designed for, and a clear statement that the result isn't a diagnosis. If those details are missing, treat an easy score as an invitation to ask better questions.
Why Language and Culture Change the Meaning of a Score
An easy English score can still be the wrong score, and fluency in English does not fix it. Every test carries assumptions about how people describe distress, and those assumptions travel poorly across languages.
Translation is not equivalence. A Hindi, Tamil, Bengali or Marathi version needs its own validation, its own examples and its own norms, because literacy and years of schooling change how a question lands. A well-made coat in the wrong size will not keep you warm, however good the stitching is.
Indian research keeps flagging this. An appraisal of the NIEPID Indian Test of Intelligence, discussed in this review of psychological assessment in India, called for systematic documentation of translation, linguistic adaptation, validation procedures and language-specific norming so users can judge cultural and linguistic equivalence for themselves. Digital tools share the same weakness: a 2025 systematic review found that few mental-health apps were developed in Asia, and that their sociocultural relevance and effectiveness in Indian settings have been insufficiently evaluated.

Four questions to ask before you trust a number
- Has this language version been validated? Translated and validated are different jobs; a version can read fluently and still be unproven.
- Does the comparison use Indian norms? A cutoff built elsewhere describes a different population.
- Could code-switching have changed my answers? Answering partly in one language and partly in another can shift how strongly you endorse an item.
- Should an English-only result stay provisional? Often yes, especially when the alternative is treating a culturally thin score as a fact about you.
Imported tools are not worthless. The label "validated" has to travel with the version you took, in the language you read. A score without that information is comparable to something, but possibly not to you.
The most accessible test is not always the most appropriate one. Convenience is a feature of the product, not evidence about your mind.
A professional review protects you here. A clinician can ask what a question meant to you, notice where your answer reflected the wording rather than your experience, and weigh the result against the rest of your life.
How to Read a Score Without Turning It into a Label
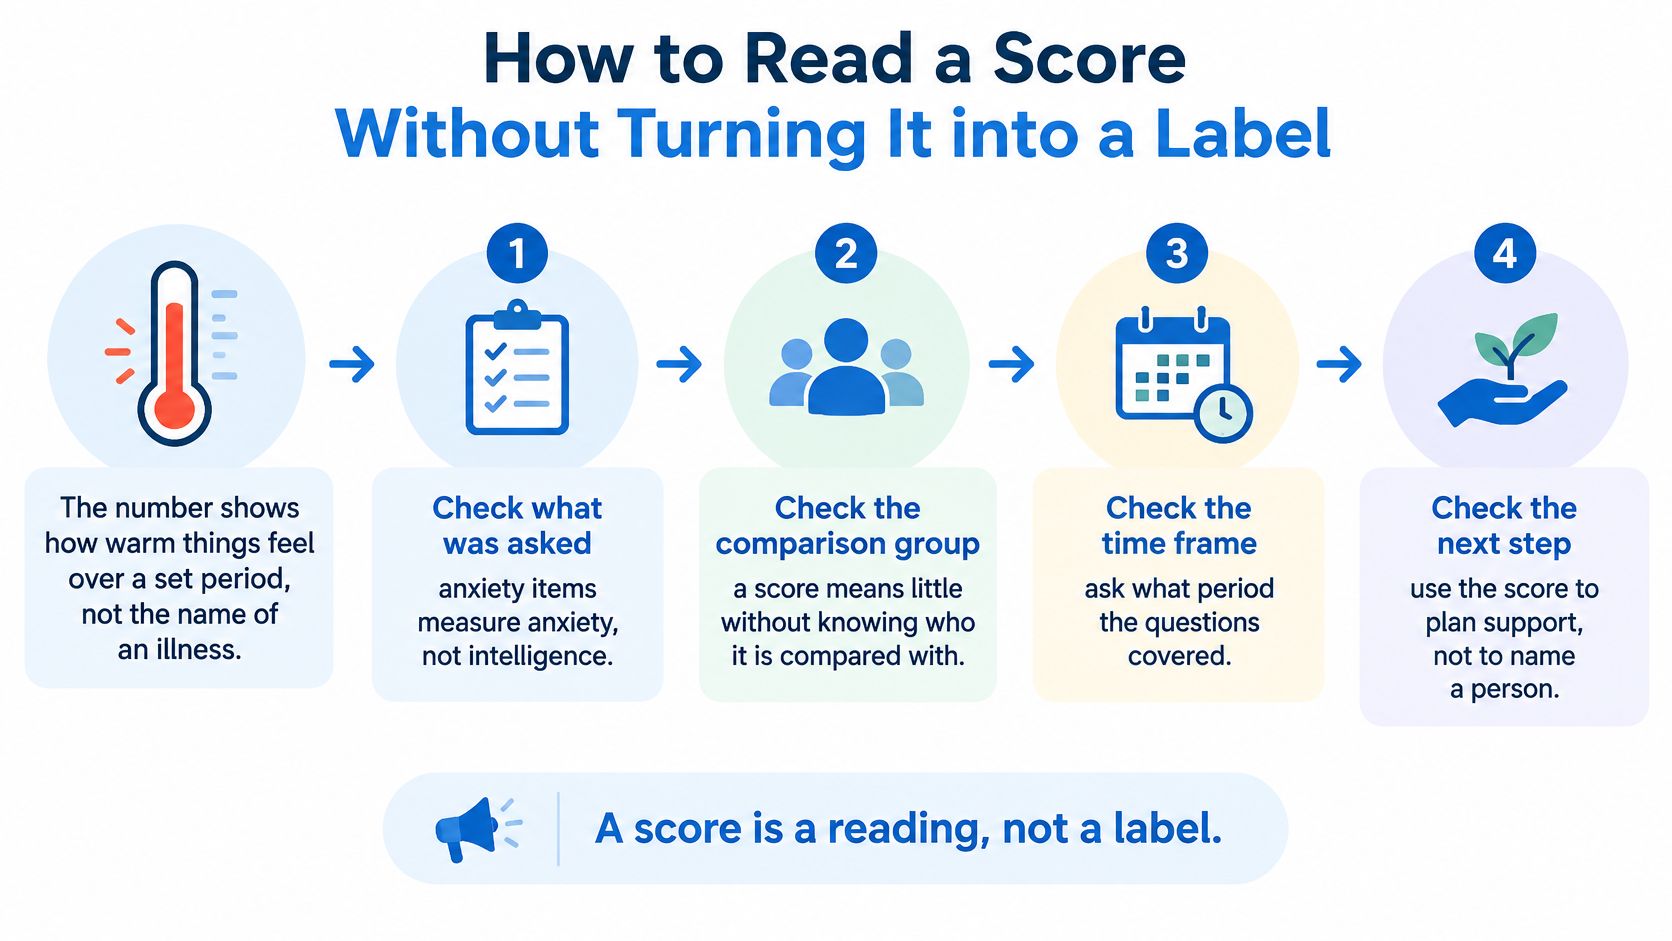
Picture a thermometer. It tells you how warm the room is right now. It doesn't name the illness behind a fever, and it doesn't forecast next month. A screening score is the same kind of instrument: a reading of conditions over a set period.
Four checks before you interpret anything
- Check what was asked. Anxiety items measure anxiety, not intelligence and not depression. A single "mental health" total smears several different experiences into one figure, and those experiences need different questions, different time frames and different kinds of help.
- Check the time window. Was the question about the past two weeks or about your whole life? A rough fortnight after a deadline describes a fortnight. It doesn't describe your personality.
- Check daily impact. Symptoms without impairment look very different from distress that stops you sleeping, studying or turning up to work. Burnout that flattens your week deserves attention even when the item count looks modest.
- Check the comparison group. A cutoff validated with one group, in one language, in one clinic can mislead someone else. Comparison is the quiet machinery behind every score, and it's the part online tools explain least. Hiring teams reading profiles across candidates run into the same problem, which is why using personality data for smarter hiring treats role and context as part of the reading rather than an afterthought.
The step that follows the score
| Result pattern | Plain meaning | Sensible next step |
|---|---|---|
| Usual range | Distress looks limited for the period asked about | Keep ordinary supports for sleep, relationships, and well-being; repeat only if life changes |
| Mild rise | Some worry, low mood, or strain is showing up | Reflect on work, study, and rest; consider a repeat screen in a few weeks |
| Moderate rise | Symptoms are affecting daily life | Talk with a qualified counsellor or therapist; do not self-label |
| High rise or safety concern | Distress is heavy, or self-harm thoughts are present | Seek urgent professional or emergency help; do not rely on the test alone |
Walk that table with one rule in mind. The higher the row, the less the next step should look like another questionnaire.
A low score can miss distress when someone plays down their answers. A high score can reflect a hard week, poor sleep or exam stress. Neither number names a person.
Automated scoring can add up items and apply a rule. It must not generate a diagnosis or a treatment recommendation. That step needs a trained human who can ask what the number can't.
After a Concerning Score and How Your Answers Stay Private
A moderate or high result can land like a stone. You answered with care, the screen returned a number, and now it is midnight and you are reading symptom lists.
Here is the steadier reading. A moderate score means your questionnaire and your daily life both deserve a human review. It stays a signal that needs interpretation. In a 2026 pilot co-designed with Indian university students, app-based DASS-21 screening agreed closely with clinician assessment, with correlations of 0.819, 0.887 and 0.972, as reported in the study published in JMIR Formative Research. The researchers still called for larger, multisite validation before broad use. Strong agreement between a screen and an interview is encouraging. It is still a screen.
A calm sequence for the next 48 hours
- Safety first. If you endorsed any item about wanting to die or being unable to stay safe, contact local emergency services or a trusted person now. Don't wait for a retest.
- Reread the items you endorsed. Say them in ordinary words, without the score attached.
- Note what else is happening. Grief, a brutal workload, poor sleep, a fight at home. A spike usually has a context.
- Share the result with a qualified clinician, who can interview you and rule out other explanations for the same answers.
- Repeat only after the tool's suggested gap, and only when there's no safety concern.
Who can see your answers
India's Digital Personal Data Protection Act is built around consent, a specified purpose, collecting only what is needed, and keeping it for a limited time. Those principles only protect you if the platform explains how they apply to your answers.
A visible privacy policy is not the same as privacy. A policy pinned to a homepage works like a lock on a gate: reassuring to look at, silent on who holds the keys. Retention, sharing, deletion and secondary use can stay unexplained even when a policy clearly exists. Before you answer, ask who inside the organisation can open your record, whether an employer or college can request it, how to ask for deletion, and whether your answers are used to train anything.
Assessments requested by someone else carry extra weight. A court-ordered evaluation follows a different path from a private self-check, because the result goes to an institution rather than staying with you, as the Georgia DUI Schools court evaluation overview describes.
Decide When to Speak with a Qualified Professional
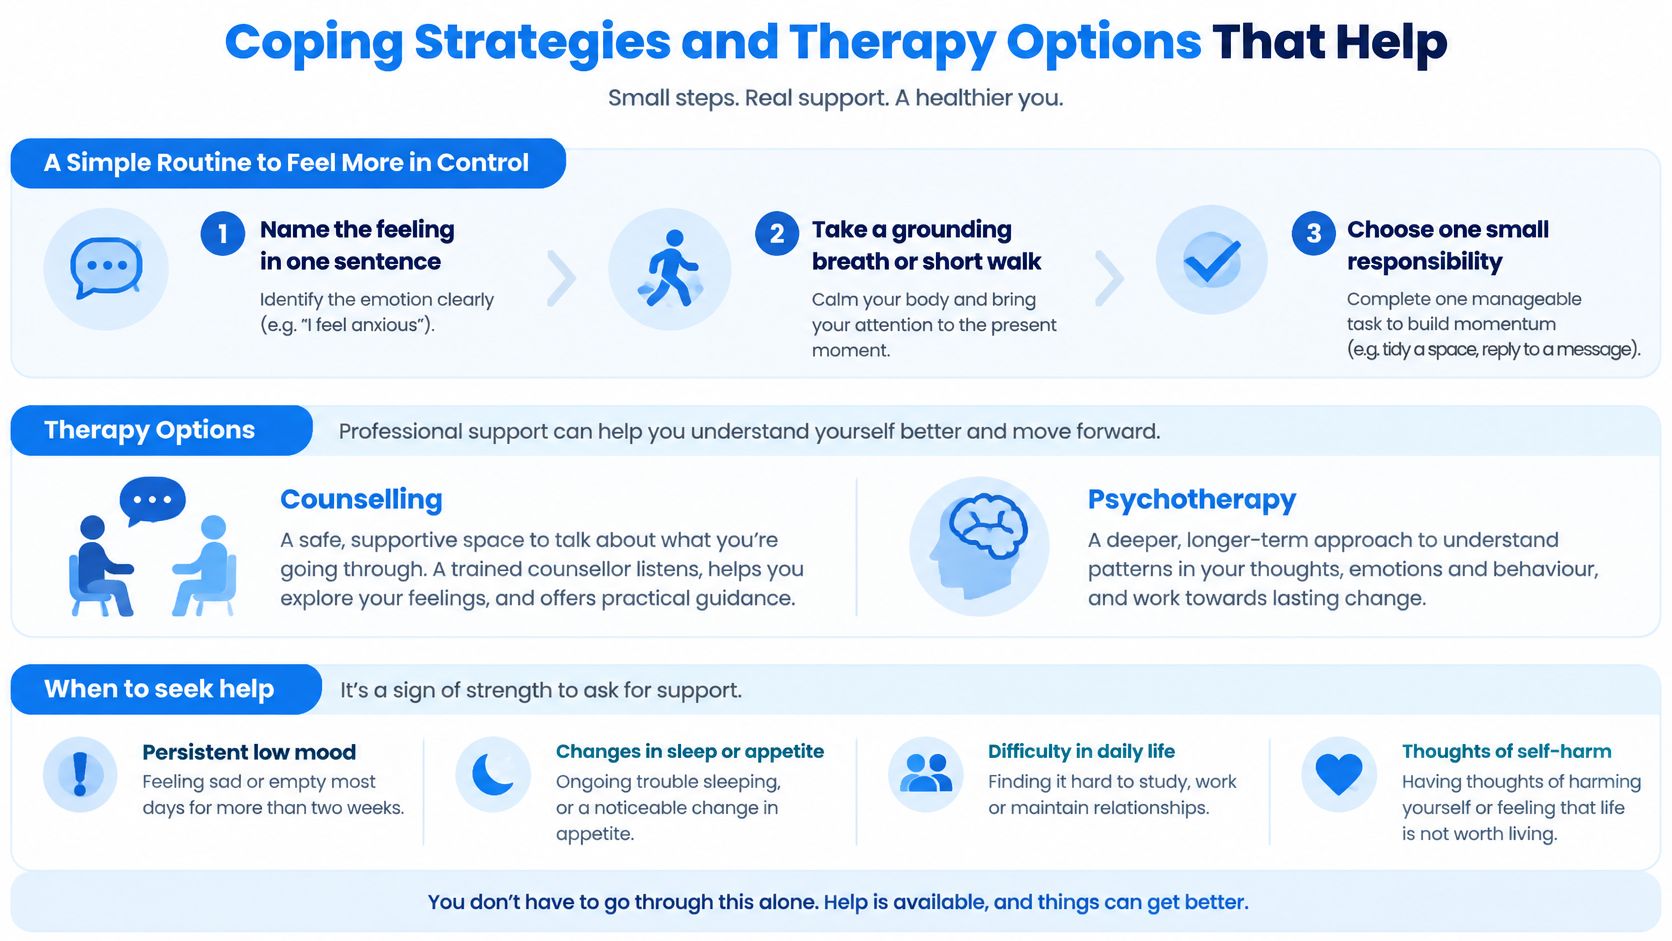
You don't need a diagnosis to deserve support. Speak with a qualified psychologist, therapist or counsellor when distress lasts more than a few weeks, when work or study is slipping, when relationships are strained, when earlier screens keep climbing, or when your safety is in doubt.
People also come for growth rather than repair. Building resilience, compassion, self-esteem and a steadier sense of happiness is a legitimate reason to book a session, and often a more motivating one.
What a professional assessment usually looks like
Expect a clinical interview first, then a small number of tools chosen for your situation, then a feedback session that explains the results in context. The order matters. A test score without an interview is a sentence without a verb.
Before you book, check two things
Look for a recognised postgraduate qualification in clinical or counselling psychology. Then ask how your results will be stored, who they'll be shared with, and how they'll be deleted.
For urgent or uncertain moments, Tele-MANAS is a free government helpline. It had handled 1,827,951 mental-health-related calls by 2025 since its 2022 launch, according to the Government of India's 2025 release.
A few takeaways to carry with you:
- A test is a conversation starter, not a verdict on your life.
- Anxiety and depression need different questions, so don't read one number as both.
- Language and norms change what a score means, which is why the version matters as much as the result.
- A concerning score deserves a person, not another label or a search spiral.
- Asking about privacy is fair, even when the assessment is free.
DeTalks is one India-based place to explore confidential, science-backed assessments and connect with psychologists, therapists and counsellors for therapy or counselling, holding the same non-diagnostic boundary.
If this piece leaves you with one useful question, make it this: which assessment fits what you're feeling, and who will read the result with you? DeTalks brings science-backed, confidential assessments together with a directory of psychologists, therapists and counsellors, so a score becomes the start of a conversation rather than a label you carry alone. Visit DeTalks to explore an assessment or book a session, and take the next step with someone qualified beside you.