
If two people have anxiety, should they automatically receive the same therapy, even when one avoids presentations and the other feels overwhelmed enough to hurt themselves? A diagnosis can help guide care, but it doesn't explain every person's most urgent treatment need.
That's the useful starting point for CBT vs DBT. Whether you're navigating exam pressure, family expectations, workplace stress or depression in India, the question isn't which therapy is better. It's which approach addresses what keeps you stuck, with support you can realistically use.
CBT and DBT at a Glance
CBT and DBT side by side
| Aspect | CBT | DBT |
|---|---|---|
| Core idea | Change the thoughts and behaviours that keep distress going | Accept distress as it is while building skills to change it |
| Main targets | Depression, anxiety, panic, OCD, insomnia | Emotion dysregulation, self-harm urges, intense anger, unstable relationships |
| Key techniques | Thought records, behavioural experiments, graded exposure, activity scheduling | Mindfulness, distress tolerance, emotion regulation, interpersonal effectiveness |
| Typical length | About 12 to 20 weekly sessions | Often 6 to 12 months, with individual therapy and a skills group |
| Session focus | Current problems, goals and homework review | Skills practice, crisis coaching and validation |
| Evidence strongest for | Depression and anxiety disorders | Emotion dysregulation and self-harm risk |
CBT changes how you think and act around a problem; DBT adds particular emphasis on managing intense emotion and crisis. Both are evidence-based talking therapies, offered by appropriately trained psychologists, therapists and counsellors across India.
The distinction isn't absolute. CBT includes work with feelings, and DBT includes work with thoughts and behaviour. DBT developed from cognitive behavioural approaches, rather than standing entirely apart from them.
Read the comparison as a starting point
The targets row describes common reasons for choosing each approach, not rules about who can receive it. A person with depression might need help rebuilding daily activity, managing overwhelming emotional reactions, or both.
Likewise, the length row describes common programme formats, not a prescription or a deadline for improvement. Brief interventions, individual needs and the availability of a full DBT team can change what treatment looks like.
Neither approach is better in general. Fit involves your main concern, your readiness for practice and the therapist's training, as well as practical issues such as privacy, language, scheduling and cost.
Practical rule: Choose the problem you want help changing before choosing the therapy acronym.
For a student, that problem might be missing classes because of fear of judgement. For a parent, it might be reacting angrily during family disagreements, then feeling ashamed afterwards.
Find the row closest to your concern and note questions to bring to counselling: which part of this approach would address my difficulty, and what would practice look like between sessions? You don't need to decide your own treatment before meeting a professional.
How Cognitive Behavioural Therapy Works
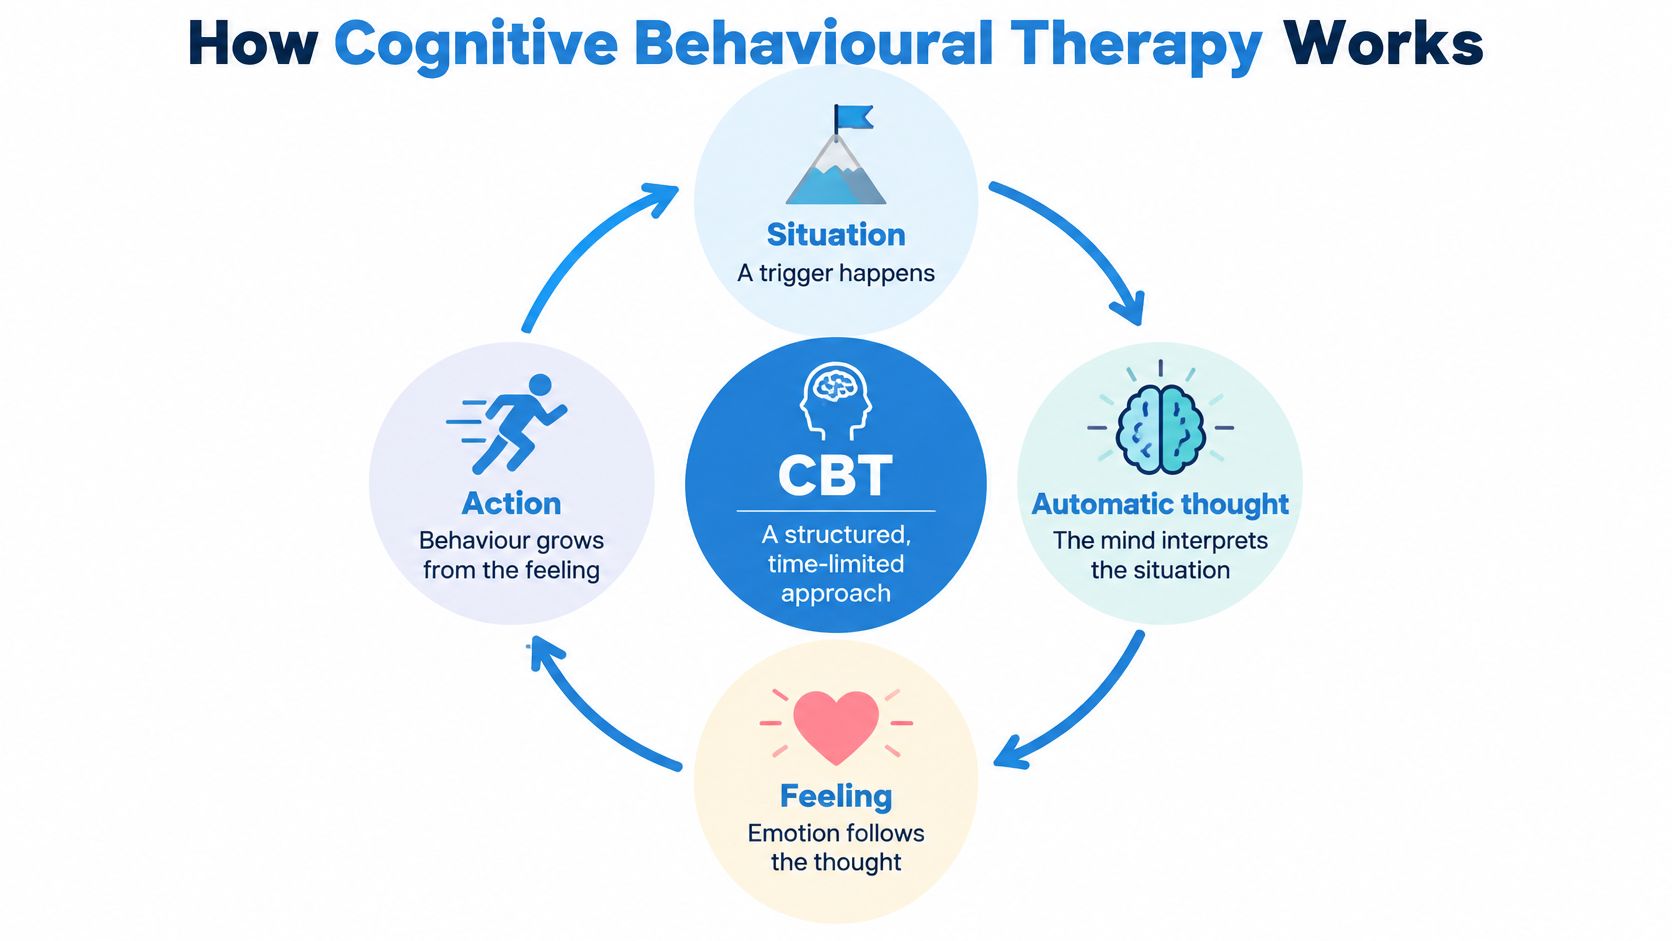
Cognitive behavioural therapy, or CBT, is a structured, usually time-limited approach that examines connections between situations, thoughts, feelings and actions. It doesn't ask you to replace painful thoughts with cheerful ones. It helps you check interpretations and try more useful responses.
A deadline arrives, and you automatically predict that you'll fail. Anxiety rises, you postpone the task, and the unfinished work makes the next deadline feel even more threatening.
This diagram shows the cycle a therapist might help you examine.
Turn the cycle into something you can test
A therapist helps identify an entry point into that cycle. You don't have to feel confident before making a small behavioural change.
- Thought records: Write down a prediction that your presentation will be a disaster, then examine supporting and contradictory evidence. A balanced conclusion might acknowledge nerves without assuming failure.
- Behavioural experiments: If you believe asking for clarification makes you look incompetent, try asking a prepared question and observe the response.
- Graded exposure: Build a manageable ladder for feared situations, such as speaking to a colleague before contributing in a meeting. Panic-focused exposure should follow an individual assessment and clinical plan.
- Activity scheduling: When low mood makes everything feel pointless, schedule a small, meaningful activity rather than waiting for motivation.
- Sleep and worry routines: Agree a consistent waking routine or a planned period for writing down worries, rather than trying to solve every concern in bed.
CBT is commonly used for depression, generalised anxiety, panic disorder, social anxiety, OCD, insomnia and workplace stress. The specific techniques should match the concern; OCD treatment, for example, needs more than general advice to think positively.
What participation involves
Treatment usually starts with shared goals, followed by practice between appointments and regular progress reviews. Homework can feel useful because you're learning usable skills, but it can also feel demanding during very low periods, so tasks should be adapted rather than treated as a test.
An Indian digital CBT programme evaluation involving 150 adults used five structured one-hour sessions and reported significant improvement on the Depression Anxiety Stress Scale-21, with p=.000 as reported. Because it compared participants before and after the programme rather than randomly comparing CBT with DBT, it supports feasibility and a signal of benefit, not superiority.
For another accessible explanation of the approach, the Vancouver CBT insights from Orange Neurosciences offer a supplementary resource. Your own therapist should still explain how their plan fits your circumstances.
This video offers another way to explore CBT.
Before starting, ask what the first homework will involve, how progress will be measured, and how many sessions the therapist expects. Those answers should describe a flexible plan, not promise an outcome.
How Dialectical Behaviour Therapy Works
Say a university student receives a hurtful message during a family argument. Their anger rises quickly, they send repeated messages, and then they feel an urge to harm themselves.
At that moment, analysing whether their interpretation is accurate may not be the first task. They may first need help getting through the emotional surge safely.
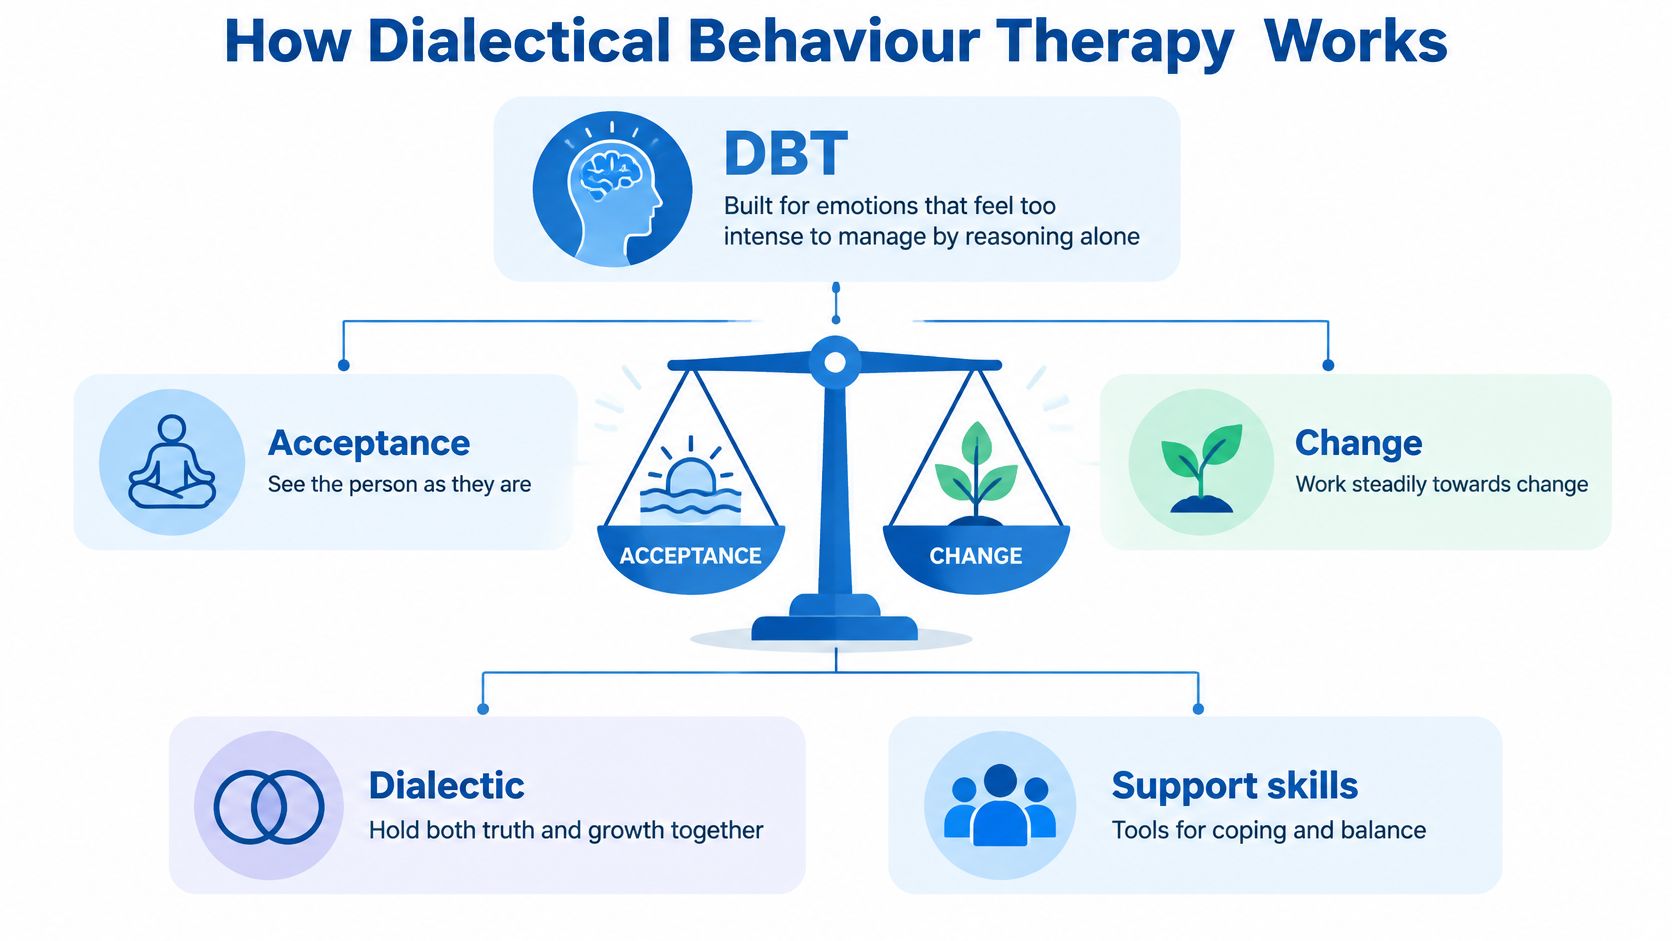
DBT's central idea is that you can accept your experience as it is and still work towards changing your response. Acceptance doesn't mean approving of harm, tolerating mistreatment or giving up.
Skills for the moment and what follows
With mindfulness, the student practises noticing anger, physical tension and urges without immediately acting on them. They might feel their feet on the floor and name what's happening, rather than treating every thought as an instruction.
Distress tolerance focuses on surviving a crisis without making it worse. TIPP refers to temperature, intense exercise, paced breathing and paired muscle relaxation; a clinician should adapt these options to the person's physical health, rather than prescribing abrupt temperature changes or vigorous exercise indiscriminately.
Emotion regulation means learning what makes emotions harder to manage and choosing responses deliberately. The student might notice that arguments become harder after poor sleep or missed meals, then plan support before another difficult conversation.
Interpersonal effectiveness helps the student ask for what they need while maintaining self-respect and considering the relationship. The DEAR MAN framework involves describing the situation, expressing feelings, asserting a request, reinforcing its value, staying mindful, appearing confident and negotiating.
Full DBT isn't the same as a skills session
DBT was first developed for borderline personality disorder and is now used more widely for self-harm, difficulty regulating emotions and some substance-use presentations. You don't need that diagnosis to discuss whether DBT skills suit your needs.
Full programmes generally include weekly individual therapy, a skills group, agreed between-session phone coaching and a therapist consultation team. Phone coaching has defined boundaries; it isn't a replacement for emergency care.
An Indian study of DBT among young adults in Punjab provided treatment to 150 young adults from 18 districts for 12–18 weeks and reported reductions in suicidal ideation, perceived burdensomeness and thwarted belongingness. These findings are encouraging, but a targeted sample without a direct CBT comparison can't establish that DBT is generally more effective.
Validation means recognising that your distress makes sense in context. It doesn't mean every action taken during distress is safe or helpful.
DBT requires time, structure, and repeated practice, and full-model care involves a team. Ask whether a provider offers full DBT, a skills group, or DBT-informed individual therapy, because those descriptions don't mean the same service.
Which Concerns Each Approach Handles Best
Starting approach by main concern
| Main concern | Usual starting fit | Why it fits |
|---|---|---|
| Persistent worry or panic attacks | CBT | Targets catastrophic thoughts and avoidance through exposure |
| Low mood and low motivation | CBT | Activity scheduling and behavioural activation rebuild routine |
| Intense emotional outbursts or quick mood swings | DBT | Emotion regulation skills aim to reduce emotional vulnerability |
| Recurrent self-harm urges or repeated crises | DBT | Distress tolerance and crisis skills, with clinician oversight |
| Workplace stress with heavy workload | CBT first | Structured problem-solving; add DBT skills if emotions escalate |
| Relationship conflict driven by reactivity | DBT | Interpersonal effectiveness scripts support clearer communication |
These are starting fits, not diagnoses or guarantees. Sudden mood changes, persistent sleep disturbance or difficulty functioning may require a broader clinical assessment before choosing a therapy plan.
The most useful question is what needs to change first. Is it avoiding situations, withdrawing from daily life, acting during an emotional surge, or remaining safe?
Different targets in everyday life
Consider a software engineer who fears having a panic attack before deadline meetings. They begin skipping calls, checking their pulse repeatedly and working late to compensate.
A CBT plan could address frightening predictions, avoidance and safety behaviours, with carefully planned exposure. If the engineer can attend meetings more consistently and reduce checking, those are concrete signs that the chosen target is changing.
Now consider a student whose anger escalates after arguments with friends. They understand later that their interpretation wasn't the only possibility, but during the argument they can't pause before sending hurtful messages.
DBT skills could help them tolerate the immediate surge and communicate a request once they're calmer. The first goal might be getting through disagreements without threatening messages or unsafe behaviour, rather than winning the argument.
Match the plan to the difficulty, not just the label
Some people need both kinds of work. A therapist might help someone manage overwhelming feelings first, then use CBT strategies to address avoidance once they can engage with those tasks.
That doesn't make a blended plan automatically better. The clinician should explain why each technique is being used and how they'll know whether it helps.
In an Indian virtual DBT skills-group trial, 43 participants received skills training and 41 joined a waitlist; the eight-week intervention retained 71.8% and lowered depressive symptoms, but didn't significantly improve emotion dysregulation, dysfunctional coping or anxiety. This mixed result is a reason to monitor individual outcomes, not assume that teaching a skill guarantees improvement in its intended target.
Workplace stress also needs context. Therapy can support boundaries and coping, but it doesn't make an unsafe workload reasonable or replace action on harassment, discrimination or inadequate staffing.
Self-harm urges, safety concerns and dissociation need prompt professional attention. If there's immediate risk, contact a local crisis helpline or emergency service immediately, or go to the nearest emergency department; don't wait for a routine counselling appointment.
What the Indian Research Shows Today
India's evidence base is stronger and broader for CBT than for DBT, particularly for common depression and anxiety concerns. That's a statement about the available studies, not a ranking of every individual's likely experience.
The 2024 systematic review of psychotherapy research in India described CBT as the country's most commonly practised evidence-based psychotherapy, including a social-anxiety trial with 50 medical students receiving six weekly two-hour sessions, whose significant gains remained at two-month follow-up, and a panic-disorder comparison involving 30 participants, 15 in each group. The review also noted that most Indian studies followed participants for only three months to one year, limiting conclusions about long-term durability.
Indian studies at a glance
| Study | Focus | Participants | Key result |
|---|---|---|---|
| Group CBT trial | Social anxiety | 50 medical students | Significant gains held at two months |
| CBT vs behaviour therapy trial | Panic disorder | 30, with 15 in each group | Comparative outcome not specified in the review summary |
| Digital CBT programme | Depression, anxiety, stress | 150 adults | Significant DASS-21 improvement, pre/post only |
| DBT-A module plus medication | Dissociative disorders | 40 adolescents | Dissociative symptoms improved at eight weeks; adaptive skills did not improve significantly |
| Virtual DBT skills group | Emotion dysregulation, depression | 43 in DBT skills training, 41 on waitlist | Lower depressive symptoms; 71.8% retained; no significant change in emotion dysregulation or anxiety |
The comparisons matter as much as the improvements. A before-and-after programme evaluation can't separate treatment effects from every other influence, while a waitlist comparison doesn't show whether another active therapy would work equally well.
The broad picture is easier to understand when the approaches are placed alongside their treatment targets.

What these findings can reasonably support
Indian CBT studies cover depression, social anxiety, panic, post-traumatic stress disorder and OCD, among other concerns. This breadth supports considering CBT as a comparatively well-established starting framework, while still checking whether the specific treatment matches the person's needs.
Indian DBT evidence remains newer, narrower and preliminary. Small or selected samples, different diagnoses and limited direct CBT comparisons make sweeping claims inappropriate.
A dissociation-focused adolescent intervention also isn't interchangeable with adult outpatient DBT or an online skills group. Different populations, treatment components and comparison groups answer different questions.
Assessments and screening tools are informational, not diagnostic. Symptom scores can help organise a conversation and track change, but a qualified clinician must interpret them alongside functioning, history and safety.
Look for a therapist who can explain both the evidence behind their approach and its limits. A candid explanation is more useful than a claim that one model works for everyone.
Choose the Right Approach and Book With Confidence
Start with a sentence about what you want to change. For example, you might want to stop avoiding team meetings, recover a daily routine after burnout, or get through conflict without acting on unsafe urges.
Then describe how intense the problem feels, how often it happens and what it interrupts. Include sleep, study, work, relationships and self-care, rather than relying only on whether you feel better or worse overall.
Use these checks before booking
- Treatment target: Is the main problem thoughts and avoidance, or emotional surges and crises?
- Safety: Are there self-harm, safety or dissociation concerns that need prompt assessment and a skills-focused safety plan?
- Practical commitment: How much time and between-session practice can you realistically manage each week?
- Therapist preparation: Is the therapist trained in the chosen model and able to explain it clearly?
- Shared review: Will you review progress together using daily-life goals and an appropriate validated scale, such as the DASS-21?
You don't need perfect answers. These questions help you and the clinician decide what deserves attention first, including whether routine outpatient therapy is the right level of support.
The checklist can help you organise those thoughts before an appointment.

Make the first appointment a collaborative conversation
Write down the main concern you want help changing, then shortlist professionals whose profiles mention CBT, DBT or both. Read their qualifications and relevant training rather than relying on an acronym alone.
Ask how they would begin with your particular difficulty. A useful answer should connect their proposed methods to something concrete, such as attending classes, reducing panic-related avoidance or staying safe during emotional distress.
You can also ask whether they combine CBT strategies with DBT skills. They should be able to explain the purpose of that combination, rather than presenting a long list of methods without a clear plan.
- Discuss the format: Clarify individual sessions, group participation, between-session contact and any limits on coaching.
- Plan a review: Ask what you'll review at four and eight weeks, without treating those points as deadlines for recovery.
- Check the commitment: Understand the expected session length, overall treatment plan and costs before paying.
At DeTalks, you can browse qualified therapists and book a consultation. Our assessments are informational, not diagnostic, and can support reflection rather than determine which therapy you need.
We do not accept cancellations and do not give refunds, so check your availability and booking details carefully before confirming. Our support team can be reached at support@detalks.com for booking-related questions.
Look beyond symptom reduction
Well-being can mean more than feeling less anxious or depressed. You may also want to build resilience, practise compassion, reconnect with meaningful activities or make room for happiness without demanding that you feel positive all the time.
Name a strength you already use when things feel hard. It might be asking a friend for help, caring for a family member, returning to a routine or noticing when you need rest.
Bring that strength into therapy alongside the problem. A compassionate plan recognises what you can already do, while making space to learn something different.
If a plan feels unmanageable or progress stalls, discuss the obstacle openly. You may need smaller tasks, a different focus, another clinician or additional care; changing direction isn't a personal failure.
Support is available in India and beyond, and resilience can grow through practice and connection. Neither CBT nor DBT promises a cure, but you can seek a thoughtful plan that respects your needs, circumstances and pace.
The best approach is usually the one you'll keep attending and practising, not the one with the most impressive name.
DeTalks brings together qualified mental health professionals so you can explore support for thoughts and avoidance, emotional overwhelm or a combination of concerns. Visit DeTalks to browse therapist profiles and book a first consultation with your main concern and questions ready.



