
Tag: depression treatment

  • Best Therapy for Anxiety and Depression Compared

    Best Therapy for Anxiety and Depression Compared

    You might be finishing work in Mumbai or Bengaluru, replaying a difficult conversation while trying to sleep, or noticing that worry and low mood are making ordinary tasks feel heavier. You want help, but searching for the best therapy for anxiety and depression can raise another question: where do you start when different options seem to promise different things?

    There isn't one treatment that suits everyone. The right next step depends on what you're experiencing, how much it affects daily life, what feels acceptable to you, and what care is available. The aim is a pathway that's evidence-based, safe, and sustainable.

    Finding the Best Therapy for Your Needs

    Consider someone who has been feeling tense, sleeping poorly, and withdrawing from friends. They may wonder whether to try counselling, an online exercise, or a doctor's appointment first. A person in a similar situation might be dealing with a specific trigger, while another may have persistent symptoms that call for a fuller clinical assessment. Their next steps need not be identical.

    “Best” doesn't mean one therapy wins every comparison. It means choosing care that fits the person's symptoms, severity, daily functioning, safety, preferences, language, budget, and access to a suitable professional. Psychotherapy can help people understand patterns and practise new ways of coping. A psychiatric evaluation can assess whether medical care, including medication, should be considered. Some people benefit from a coordinated combination, while structured self-help may be a starting point for suitable mild difficulties.

    India's National Mental Health Survey found that 85.2% of people with major depressive disorder and 84.0% of people with anxiety disorders weren't receiving appropriate treatment, underscoring the importance of accessible professional support (National Mental Health Survey findings). Seeking help is a responsible step, not a sign of failure.

    Treatment pathway Main purpose When it may be considered Important boundary
    Structured self-help Practise coping skills and build awareness Mild concerns, with no immediate safety risk It isn't a substitute for diagnosis or needed clinical care
    Psychotherapy or counselling Work with a professional on thoughts, feelings, behaviour, and life difficulties Anxiety, low mood, stress, or relationship concerns Fit, training, access, and follow-up matter
    Psychiatric evaluation Assess symptoms and medical treatment options Persistent, severe, complex, or safety-related concerns Medication decisions require a qualified clinician
    Combined care Coordinate psychological and medical support When a clinician considers both approaches appropriate Providers should communicate and review progress

    If anxiety seems connected to life-stage changes, a focused resource on anxiety during perimenopause may help you prepare questions for a healthcare professional. An online assessment can also help organise observations before an appointment, but assessments are informational, not diagnostic. Start by understanding the options, compare them in context, and make the next decision with safety and professional guidance in mind.

    Understanding Anxiety, Depression and Care Options

    Anxiety and depression can range from temporary distress to symptoms that persist and interfere with daily life. Stress, workplace strain, burnout, poor sleep, grief, and relationship difficulties can overlap and affect mood without automatically meaning someone has a mental-health disorder.
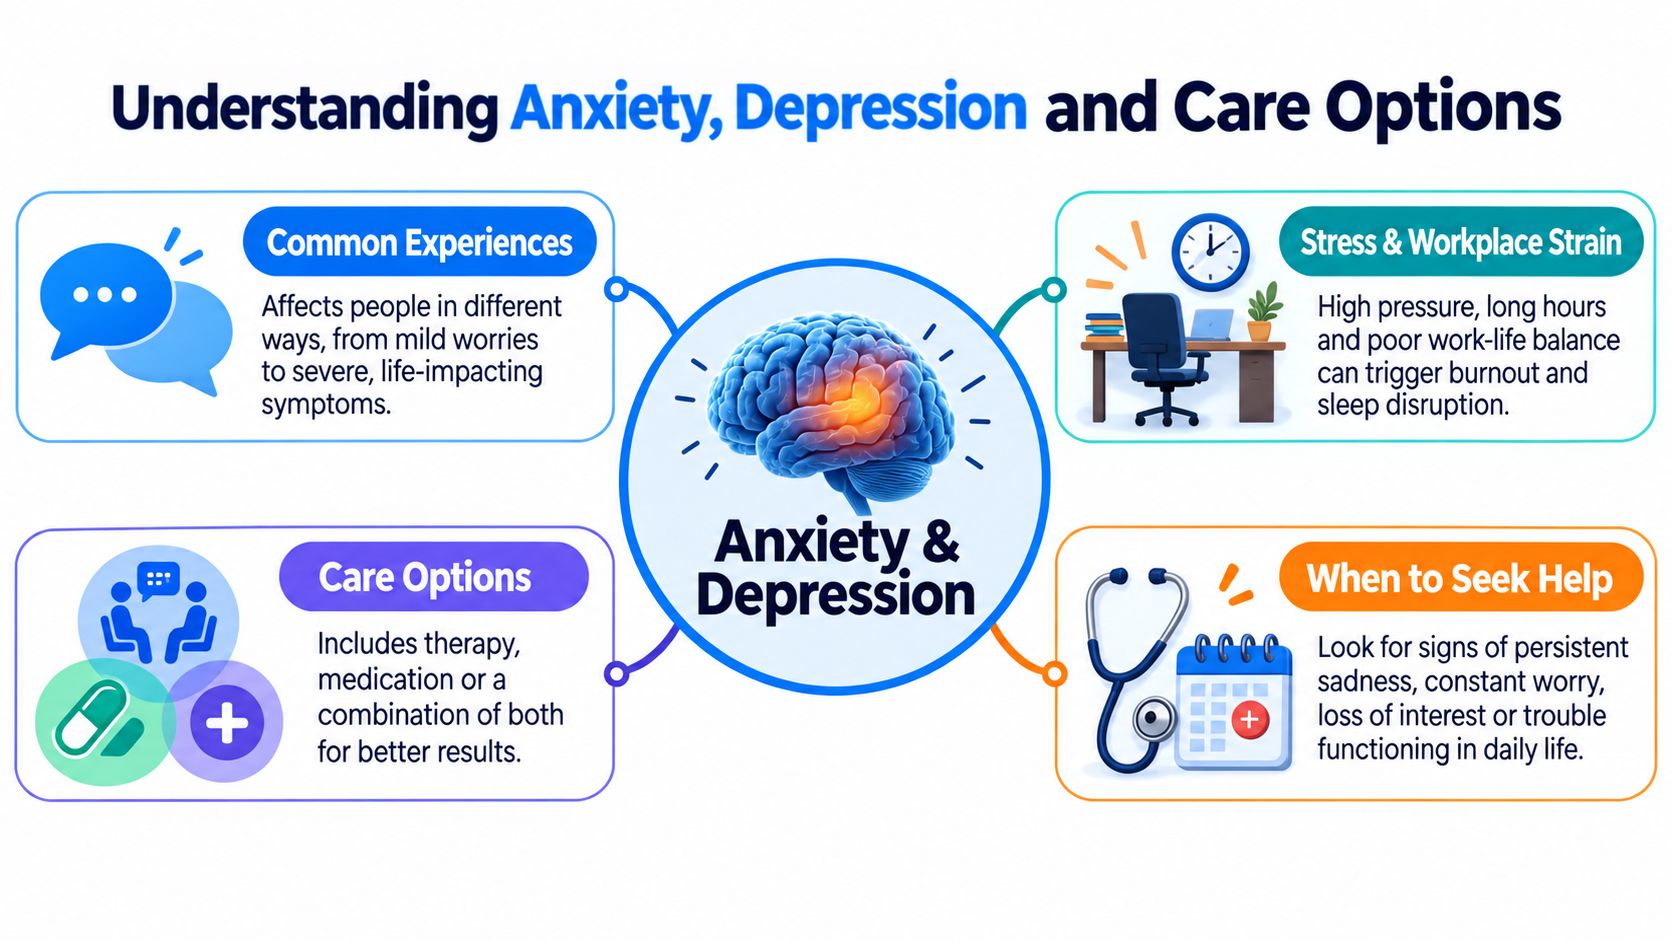
    An infographic titled Understanding Anxiety, Depression and Care Options, illustrating causes, symptoms, and potential treatment approaches.

    Therapy is a broad term for working with a trained professional on emotional or behavioural difficulties. Counselling often describes supportive conversations focused on particular concerns, though the terms can overlap in practice. Psychotherapy is psychological treatment; psychiatric care involves medical assessment and may include medication. A clinician can recommend one approach or coordinate both.

    Analysis of India's National Mental Health Survey estimated current common mental disorders at 5.1% of the population, with an overall treatment gap of 80.4% (analysis of NMHS data). This points to a practical distinction: knowing that distress is common doesn't tell an individual what treatment they need. A professional assessment considers the person, not just a label or screening score.

    What different approaches focus on

    Cognitive behavioural therapy (CBT) helps people notice connections between thoughts, feelings, and actions, then practise changing unhelpful patterns. Behavioural activation focuses on gradually reconnecting with meaningful activities when low mood has led to withdrawal. Interpersonal therapy explores how relationships, grief, and changes in social roles may affect mood.

    Practices associated with positive psychology, such as gratitude, compassion, mindfulness, purpose, and resilience-building, can support well-being. They can be part of a broader plan, but shouldn't be presented as a replacement for professional treatment when symptoms are persistent, severe, or affecting safety.

    A clinician needs to understand how long symptoms have lasted, how much they affect functioning, and whether there are safety concerns. Online screening may help someone describe what they've noticed, but it cannot diagnose anxiety or depression. The distinction matters: a tool can help start a conversation, while a qualified professional evaluates what's happening and what care may be appropriate.

    Comparing Evidence-Based Therapies for Both Conditions

    Different therapies work in different ways. CBT examines how thoughts, feelings, and behaviour reinforce one another. For example, someone who fears a work presentation may avoid preparing, feel temporary relief, and then become more anxious as the presentation approaches. In therapy, they can work with a clinician on the thinking and avoidance patterns that keep the fear going.

    Other approaches may suit different concerns. Behavioural activation can help when low mood has narrowed someone's routine and reduced contact with valued activities. Interpersonal therapy may be relevant when grief, relationship conflict, or a difficult role change is closely linked with depression. A qualified therapist can discuss the approach, explain what sessions involve, and consider whether it fits the person's goals and circumstances.

    Therapy Core approach Potential fit Evidence context Practical considerations
    CBT Works with patterns in thinking and behaviour Anxiety, avoidance, or recurring unhelpful patterns Indian guidance supports its use, with study results varying by condition Participation includes practising agreed skills between sessions
    Behavioural activation Builds engagement with meaningful activities Low mood and withdrawal Often used as a structured psychological approach The plan should be manageable and shaped with support
    Interpersonal therapy Addresses relationships, grief, and social roles Depression linked with interpersonal difficulties A recognised therapy, with suitability determined clinically Sessions may involve discussing emotionally difficult experiences
    Combined psychotherapy and medication Pairs psychological work with medical treatment When a clinician considers both appropriate Evidence depends on the condition and the populations studied Requires coordination, follow-up, and clear responsibilities

    Indian Journal of Psychiatry guidance reports 12-week response rates of approximately 70% for CBT alone, 66% for CBT plus a serotonin-reuptake inhibitor, and 49% for a serotonin-reuptake inhibitor alone. These figures are context, not a universal head-to-head scorecard: the evidence reviewed includes studies of particular disorders and populations, so it doesn't predict an individual's outcome (Indian CBT guidance).

    Fit is more than the therapy label

    A person who can attend regular sessions may value structured, therapist-led CBT and the chance to discuss progress in detail. Someone who faces travel, cost, limited privacy, or a shortage of local providers may need to explore a different format or a more accessible starting point. Online, telephone, and self-guided options can remove practical barriers, but the suitability and support offered should be considered rather than assumed.

    Therapy quality, the relationship with the professional, cultural relevance, attendance, and follow-up all matter. Ask what the proposed approach involves and how the provider will review whether it's helping. For a simple way to organise racing thoughts before a conversation with a clinician, the SleepHabits guide to quieting your mind may offer a useful reflection prompt. It isn't a substitute for care when distress is persistent or worsening.

    Choosing Between Therapy, Medication and Combined Care

    Psychotherapy, medication, and combined care have different roles. Therapy offers structured work on coping, behaviour, and emotional patterns. Medication may be considered after a psychiatric assessment, particularly when symptoms are moderate or severe, persistent, recurrent, or linked with safety concerns. Some people may start with psychological care alone; others may need medical input from the outset.
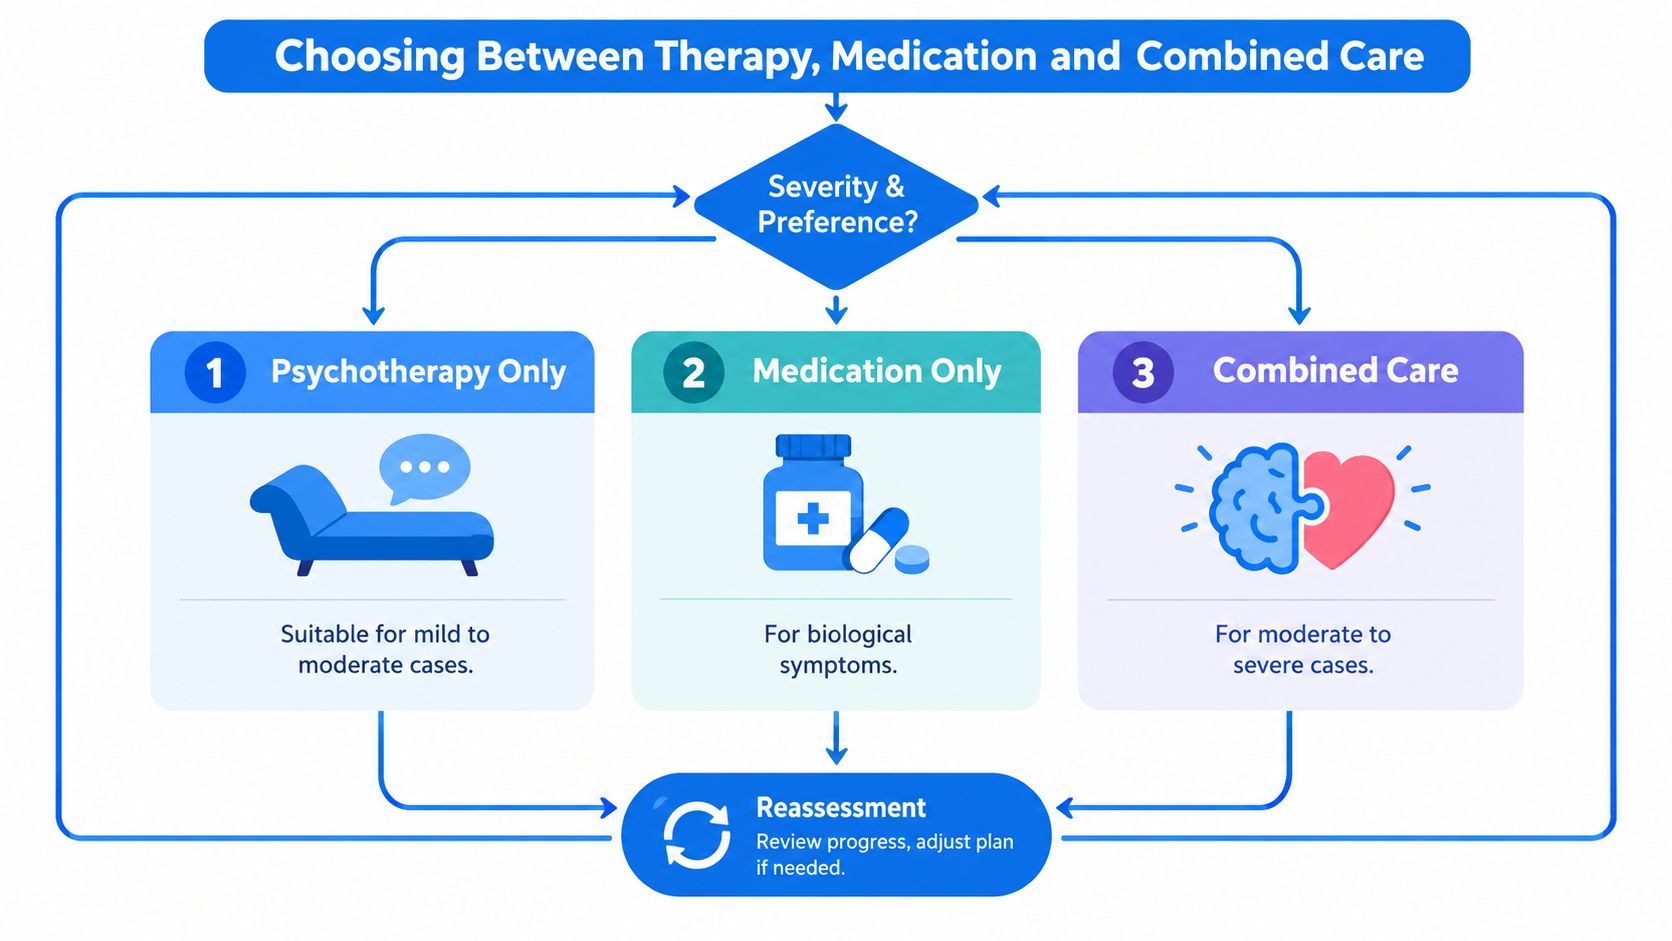
    A flow chart illustrating the decision-making process for choosing between psychotherapy, medication, or combined care for mental health treatment.

    Combined care doesn't mean the treatments are interchangeable. A therapist and psychiatrist may contribute different expertise to a shared plan. For example, therapy can address avoidance or withdrawal, while a psychiatrist assesses medication and monitors its effects. The plan should reflect the individual's needs and be reviewed when symptoms or circumstances change.

    Use stepped care, not guesswork

    A stepped approach matches the level of support to the person's needs. Suitable mild difficulties may call for psychoeducation, structured self-help, or low-intensity support. Persistent or more disruptive symptoms may require a licensed therapist, psychiatric review, or coordinated care. Behavioural activation can be part of structured psychological support, but it shouldn't delay assessment when symptoms are severe or risk is present.

    The Indian Council of Medical Research guidance notes that improvement with antidepressants may begin around week 2, with an adequate response generally assessed by about week 6 (ICMR guidance on anxiety disorders). That timeline is a guide for clinical follow-up, not a reason to start or change medication independently. If improvement is limited, a clinician can reassess the plan and consider other support, including CBT where appropriate.

    Medication selection, dose changes, interactions, monitoring, and discontinuation belong with a psychiatrist. Don't stop or adjust a prescription on your own. Resilience-building, mindfulness, compassion, and activities that support well-being can complement treatment, but they shouldn't distract from addressing significant symptoms or arranging medical care when needed.

    Matching Treatment to Real-Life Situations

    A working professional in Bengaluru whose deadlines have begun eroding sleep and mood may benefit from counselling that addresses coping skills and boundaries. Individual support has limits, though. Gallup's India country data reports that 28% of employees experienced substantial stress on the previous day (Gallup India workplace data). When stress is that widespread, employers share responsibility for workload and working conditions rather than placing it entirely on the employee.

    A man sits at a desk looking stressed while checking sleep data on his smartphone with a therapist visible behind him.

    The right question changes with the situation. Someone with recurring panic or avoidance could ask a therapist whether structured CBT is suitable and what practice between sessions would involve. A student distressed before exams might describe how sleep, concentration, and everyday tasks are affected, then discuss whether short-term counselling or a fuller assessment fits better.

    When anxiety and depression overlap

    Low mood alongside persistent anxiety rarely sorts itself into two neat categories. An integrated assessment lets a clinician identify which symptoms are most disruptive, whether daily functioning is affected, and whether psychiatric input belongs in the plan. The plan can then be revised as the picture becomes clearer, which is common when the two conditions feed each other.

    When access shapes the choice

    What is realistic matters as much as what is ideal. A review of Indian care constraints describes a shortage of trained psychosocial professionals, the concentration of private services in cities, and barriers linked to out-of-pocket costs and limited insurance reimbursement (review of mental-health access in India). Someone outside a metro might explore a telephone or video appointment, a therapist who speaks their preferred language, or a community pathway. Formats differ in the evidence and support behind them, so it is reasonable to ask how care is delivered and when referral happens.

    A plan a person can continue often serves them better than a theoretically stronger option they cannot reach or afford. Treatment works best when tied to goals that matter in daily life, such as feeling steadier, rebuilding relationships, and managing work. Those outcomes give progress conversations a practical anchor without turning well-being into a promise of cure.

    Starting Therapy Through a Clear Decision Process

    Before an appointment, note what has changed and what you want help with. This gives a professional a practical starting point and can make it easier to explain concerns when finding the right words feels difficult.
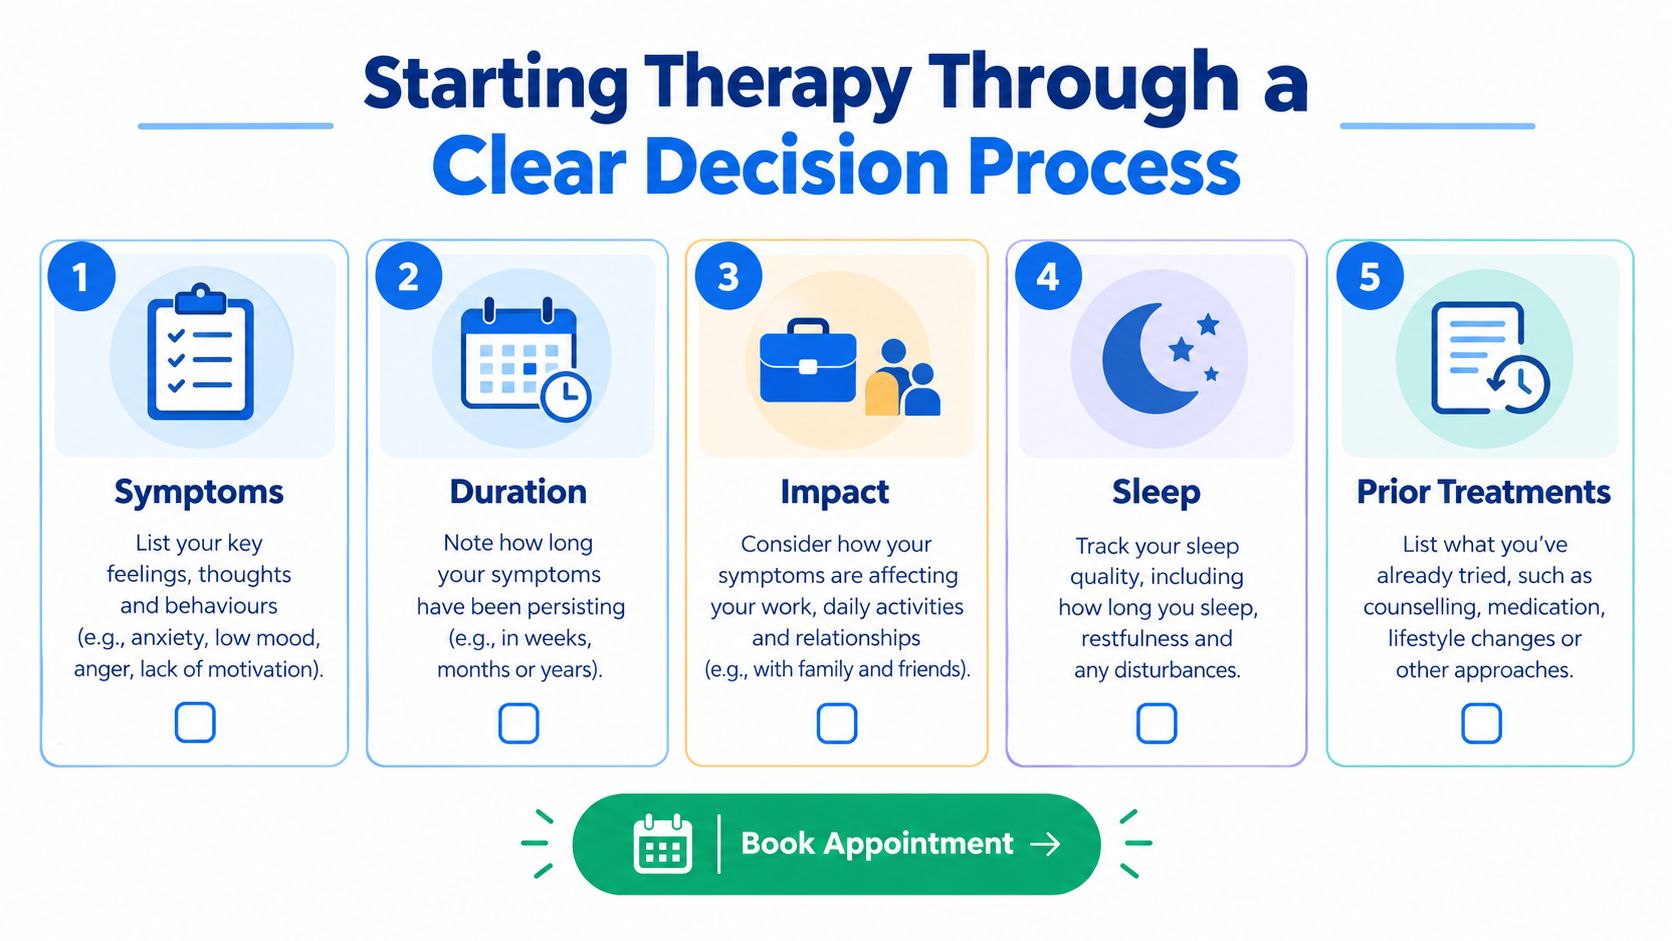
    A five-step guide on how to start therapy, focusing on symptoms, duration, impact, sleep, and previous treatments.

    Prepare information that helps a clinician

    • Symptoms: Note changes in mood, worry, motivation, or behaviour.
    • Duration: Describe when the difficulties began and whether they come and go.
    • Impact: Explain how work, study, relationships, or daily tasks are affected.
    • Sleep and health: Mention sleep changes, current medicines, and alcohol or other substance use if relevant.
    • Previous support and preferences: List what you've tried, your preferred language and session format, budget, privacy needs, and any immediate safety concerns.

    Use this information to discuss the level of care that makes sense. Self-guided or low-intensity support may be a starting point for suitable mild concerns, but persistent symptoms that interfere with daily functioning warrant professional discussion. Ask whether a licensed therapist, psychiatric evaluation, or coordinated care is appropriate.

    When choosing a provider, check their qualifications and experience, ask about their approach, and confirm fees, availability, language, confidentiality, and how sessions are delivered. You can also discuss what you hope will change and how you'll review progress together.

    Language access is part of whether care is usable. A systematic review of 350 mental-health apps available to Indian users found that only 2.9% offered an Indian language in addition to English (review of mental-health apps for Indian users). If English isn't the language in which you can most comfortably discuss personal concerns, ask about alternatives before beginning. Also consider privacy and connectivity when choosing between video, audio, text, or telephone sessions.

    DeTalks offers a directory to explore psychologists, therapists, counsellors, and other mental-health professionals in India, alongside assessment and screening tools. These assessments are informational, not diagnostic; a qualified professional needs to interpret concerns and recommend care. Use any screening result to prepare for a conversation, not to diagnose yourself or decide on medication.

    Recognising When Anxiety or Depression Needs Urgent Care

    Self-help and online screening can support reflection, but neither should become the response to immediate danger. Seek urgent help if you're thinking about suicide, have a plan or intent to harm yourself, feel unable to stay safe, experience psychosis or severe confusion, face an urgent risk related to substance use, or notice symptoms worsening rapidly.

    In India, contact local emergency medical services or go to a nearby emergency department. Tell a trusted person what's happening and ask them to stay with you while help is arranged. Don't wait for an assessment result, a scheduled therapy session, or a self-help exercise to address immediate danger.

    For urgent concerns that aren't immediately life-threatening, arrange a same-day or early psychiatric assessment where possible. A clinician can evaluate what support is needed and help determine the safest next step.

    India's National Mental Health Survey estimated an 85.0% treatment gap for common mental disorders, reinforcing the importance of making professional care easier to reach (National Mental Health Survey treatment-gap findings). That wider access challenge doesn't make an urgent warning sign less important. Needing immediate support isn't something to be ashamed of: urgent care protects safety, while longer-term therapy can address underlying patterns.

    Building Resilience Through Consistent Therapy

    Therapy works best as an ongoing collaboration rather than a fixed prescription. Attend sessions where possible, try agreed practices between appointments, and speak openly about side effects, barriers, or stalled progress. If a therapist or approach doesn't feel like a good fit, raise that directly instead of continuing unchanged.

    Ask what the plan is meant to improve and how progress will be reviewed. You can also ask whether maintenance sessions might help after symptoms ease, or when a second opinion or combined care with medication deserves consideration. Questions like these turn treatment into a shared process, which matters in India where follow-up care can be irregular and people often stop attending once acute distress settles.

    Support well-being beyond the session

    Small, compassionate habits can reinforce what happens in the room: regular meals and sleep routines, manageable movement, time with people you trust, and realistic boundaries at work or home. Gratitude or mindfulness practices may help when they fit your preferences and beliefs. These habits complement therapy; they do not replace professional support for significant or persistent anxiety or depression.

    Workplace stress deserves a wider lens. Individual counselling can support coping and recovery, yet sustainable change also depends on employers addressing workload and working conditions, a conversation worth starting if work strain is a main driver of your symptoms.

    Resilience is a capacity that grows with support. It develops as people find care that fits, build connection, and regain everyday functioning. If anxiety, depression, burnout, or exhaustion is affecting your life, speaking with a qualified professional is a reasonable first step. A single appointment can bring clarity and safety, even when the path ahead takes adjustment.


    Explore DeTalks to browse mental-health professionals and counselling options, and use its screening tools to organise what you'd like to discuss. Treat any assessment as informational, not diagnostic, and bring your concerns to a qualified professional who can help you choose a suitable next step.

  • Psychologist vs Psychiatrist for Depression: How to Choose

    Psychologist vs Psychiatrist for Depression: How to Choose

    You're sitting with your phone in your hand, searching for help because getting out of bed has started to feel difficult, work no longer feels manageable, or your thoughts keep circling the same painful concerns. Then another question appears: should you book therapy with a psychologist or consult a psychiatrist about medication?

    The answer isn't a contest between two professions. It's a practical decision based on your symptoms, safety, daily functioning, medical history, and access to care. In India, that decision is also shaped by a serious shortage of mental-health professionals, so the most realistic starting point may be the qualified provider you can reach soonest, with referral when your needs change.

    Understanding the Two Professionals

    Riya has been feeling low for several weeks. She's withdrawn from friends, is struggling to concentrate at work, and has stopped doing things she once enjoyed. She isn't sure whether she needs a counselling session, a medical appointment, or both.

    A psychologist is trained primarily in talk therapy, behavioural interventions, and psychological assessment. For depression, a psychologist may help someone understand patterns of thinking, rebuild daily routines, work through grief or relationship stress, and develop coping skills through approaches such as cognitive behavioural therapy, interpersonal therapy, or behavioural activation.

    A psychiatrist is a medical doctor specialising in mental health. Psychiatrists can assess and diagnose mental-health conditions, consider physical or medication-related contributors, prescribe antidepressants when appropriate, and manage treatment when symptoms are severe or medically complicated.

    The simple distinction: psychologists mainly provide psychological therapy and assessment. Psychiatrists provide medical evaluation and can prescribe medication.

    In India, a clinical psychologist may have training such as an M.Phil in Clinical Psychology or a Psy.D, alongside the registration required for practice. A psychiatrist generally completes an MBBS followed by an MD in Psychiatry. Exact qualifications and registration should always be checked before booking.

    A comparison chart showing the differences between psychologists, who provide talk therapy, and psychiatrists, who provide medical treatment.

    India's access problem makes this distinction especially important. The National Mental Health Survey found that 10.6% of Indian adults had a diagnosable mental disorder, with lifetime prevalence at 13.7%, and reported a treatment gap of 70% to 92%. Government reporting also notes only 0.75 psychiatrists per 100,000 people, compared with the WHO-referenced benchmark of 3 per 100,000. These figures come from the Government of India's mental-health reporting.

    That shortage means the psychologist-vs-psychiatrist decision is often a triage question, not a perfect theoretical choice. You might begin with a psychologist for structured therapy and be referred to a psychiatrist if medication, medical assessment, or urgent support becomes necessary.

    Training and How Each Assesses Depression

    The two professionals look at depression through different but complementary lenses. A psychologist's assessment usually explores emotions, thoughts, behaviour, relationships, stressors, coping patterns, and the effect of symptoms on daily life.

    A psychiatrist also asks about mood, sleep, appetite, motivation, concentration, anxiety, substance use, and safety. Because psychiatry is a medical speciality, the assessment can also consider physical contributors, medication side-effects, substance effects, or symptoms that may point towards another condition.

    What a psychologist may explore

    A psychologist may use a structured clinical interview, behavioural observation, and validated screening tools such as the PHQ-9 or Beck Depression Inventory. These tools can organise information about symptom intensity, but they don't replace a professional evaluation.

    The psychologist may also develop a formulation, which is a working explanation of how your thoughts, behaviours, relationships, history, and current circumstances interact. If there are concerns about attention, memory, learning, or cognitive functioning, psychological or neuropsychological testing may be considered.

    What a psychiatrist may add

    A psychiatrist's evaluation includes a psychiatric interview and a medical review. They may assess whether symptoms fit diagnostic criteria used in systems such as the ICD or DSM, while also considering physical health and medication history.

    Neither assessment is automatically “better”. One offers detailed psychological understanding, while the other adds medical diagnosis, risk assessment, and prescribing authority.

    Aspect Psychologist Psychiatrist
    Core training Psychology training, with clinical or counselling specialisation Medical training followed by specialist psychiatry training
    Primary focus Thoughts, emotions, behaviour, relationships, and coping Mental health diagnosis, medical factors, risk, and medication
    Assessment style Interviews, behavioural observation, screening scales, and psychological testing Psychiatric interview, medical review, diagnosis, and medication evaluation
    Depression treatment Psychotherapy, behavioural interventions, and counselling Medication management, medical care, and referrals for therapy
    Can prescribe medication Generally no Yes
    When collaboration helps When therapy needs medical support or symptoms persist When medication works alongside ongoing psychotherapy

    Training shortages have been documented for years. A 2013 Government of India release on the National Mental Health Programme listed 11,500 psychiatrists required versus 3,800 available, and 17,250 clinical psychologists required versus 898 available. The imbalance helps explain why coordinated care, tele-mental health, and referral pathways matter in India.

    What Treatment Looks Like With Each Professional

    Treatment feels different depending on whom you see first. With a psychologist, the work is usually conversational but structured. You may discuss recent situations, identify patterns, practise new responses, and agree on small activities between sessions.

    Psychotherapy can include CBT, interpersonal therapy, behavioural activation, or other evidence-based approaches. The focus might be rebuilding sleep and daily routines, reducing avoidance, challenging harsh self-judgements, improving communication, or processing a difficult life event.

    Sessions are often regular, with progress reviewed over time. Therapy requires participation between appointments, and its benefits may build gradually. That can feel demanding when motivation is low, but it also gives you skills that can support long-term well-being.

    A psychiatrist's first appointment usually centres on symptom history, diagnosis, safety, medical context, and whether medication could help. Follow-up appointments review changes in mood, sleep, appetite, anxiety, functioning, and side-effects, allowing the treatment plan to be adjusted.

    The practical trade-off

    Therapy is time-intensive and depends on a good working relationship with the psychologist. It generally doesn't involve medication side-effects, but it may feel frustrating if symptoms are so severe that you can't engage consistently.

    Medication can be important when depression is moderate or severe, when functioning has deteriorated, or when a person needs medical stabilisation. It requires monitoring, patience, and honest communication about unwanted effects. Never start, stop, or change an antidepressant without speaking with the prescribing doctor.

    Indian clinical guidance places psychotherapy most often as an initial treatment for minor depression and mild-to-moderate major depression, while antidepressants are usually preferred when medication is needed for mild, moderate, or severe depressive episodes. The Indian clinical practice guidelines explain this treatment distinction.

    A comparison chart showing how treatment differs between psychologists who offer talk therapy and psychiatrists who prescribe medication.

    For moderate or severe depression, combined care is often practical. A psychiatrist can manage medication while a psychologist provides regular therapy, provided both professionals communicate and the person understands who is responsible for each part of care.

    Typical Depression Care Pathways in India

    A person in a smaller Indian city may find a psychologist nearby, while psychiatric appointments are available only through a visiting specialist, telehealth service, or distant hospital. That reality makes depression care a triage decision, not just a choice between two job titles. Stepped care starts with support that matches current needs and adds specialist input when symptoms persist, worsen, or affect safety.

    The opening step can include psychoeducation, self-help resources, lifestyle support, or brief counselling. A psychologist, counsellor, primary-care doctor, community service, or trained tele-mental-health professional may help clarify what is happening and whether structured treatment or medical assessment is needed.

    A flexible staircase

    1. Early information and support: Learn about depression, track symptoms, involve someone you trust, and strengthen sleep, meals, activity, and daily routine.

    2. Brief counselling or structured therapy: For mild or uncomplicated symptoms, a psychologist may provide behavioural activation, CBT-informed work, or another suitable therapy approach.

    3. Review when progress is limited: If symptoms continue, interfere more with daily life, or raise questions about the diagnosis, psychiatric consultation can add medical assessment and discuss medication.

    4. Ongoing coordinated care: Therapy and medication may continue together. Follow-up can then be adjusted according to symptom response, risk, side-effects, and personal circumstances.

    The ICMR Standard Treatment Workflows for depression describe a stepped approach. For mild depression, care may begin with behavioural activation, brief counselling, yoga or meditation, and frequent follow-up. If there is no improvement in 4 to 6 weeks, pharmacotherapy may be considered. For moderate or severe depression, SSRIs such as escitalopram or fluoxetine are commonly used. Improvement may begin around the second week, adequate response is assessed by about six weeks, and continuation treatment typically lasts 6 to 9 months.

    District Mental Health Programme services, government hospital psychiatry OPDs, medical colleges, and tele-mental-health services may all form part of this pathway. Availability differs by location, so ask a local hospital how referrals work rather than assuming every service is offered in the same way.

    In tier-2 and tier-3 cities, a local psychologist may provide regular therapy while a visiting or tele-psychiatrist reviews medication and risk. Scheduling, records, referrals, and follow-up can also be supported by digital systems. Organisations building this infrastructure may seek clinical software development support to set up healthcare technology responsibly.

    Coverage depends on the public scheme, hospital, insurer, policy terms, and referral rules. Ask about Ayushman Bharat eligibility, outpatient coverage, therapy limits, psychiatric consultations, and reimbursement before relying on a service.

    A visual chart titled India's Stepped-Care Pathway for Depression showing five progressive levels of mental health support.

    Matching the Right Professional to Your Situation

    Choosing a first appointment is a triage decision, especially where India's mental-health workforce is unevenly distributed. Severity matters, but so do the symptom pattern, speed of change, daily functioning, physical health, previous treatment, and any safety concern. The aim is to start with the right level of support and make referral easier if the picture changes.

    Three situations

    Mild and recent symptoms: You feel low, disconnected, or unmotivated, yet you can manage basic responsibilities and have no thoughts of harming yourself. A psychologist is often a sensible starting point for therapy, behavioural activation, routine-building, and emotional support.

    Moderate symptoms with partial functioning: Sleep is disrupted, rumination continues, work or study is becoming difficult, and you are withdrawing from people. A psychologist and psychiatrist may need to work together. If therapy brings limited improvement after 4 to 6 weeks, medication can be considered alongside therapy, following the assessment and care plan made by a qualified professional.

    Severe or high-risk symptoms: Active suicidal thoughts or plans, psychotic symptoms, extreme agitation, catatonia, sudden loss of functioning, or signs that could indicate bipolar disorder call for urgent psychiatric or emergency assessment. Weekly talk therapy alone should not be the only response when safety, reality testing, or basic functioning is seriously affected.

    Severity Typical presentation Recommended starting professional Treatment focus Escalation trigger
    Mild Low mood, reduced interest, manageable disruption Psychologist or qualified counsellor Therapy, behavioural activation, counselling, routine support Symptoms persist, worsen, or significantly affect daily functioning
    Moderate Sleep and concentration problems, rumination, partial functioning Psychologist with psychiatric referral, or both Structured therapy, review of medication need, coordinated care Limited response, worsening function, medical complexity, or safety concerns
    Severe Serious impairment, suicidality, psychosis, catatonia, or possible bipolar features Psychiatrist or emergency service urgently Safety planning, medical assessment, medication, and higher-level care Immediate emergency support when danger is imminent

    The table is a starting guide, not a diagnosis. An assessment tool can help organise what you are noticing, but it remains informational, not diagnostic. A qualified professional must interpret the full picture, including medical history and safety.

    Workplace stress can complicate the choice. A review of workplace mental health research in India reports wide variation in depression, anxiety, and workplace-stress findings across Indian studies. Therapy can address boundaries, burnout, anxiety, and coping. A psychiatrist may be needed when symptoms become severe, functioning drops sharply, or a medical component needs assessment.

    Practical Guidance for Referrals and First Sessions

    You don't need to arrive at the first appointment with the correct label. Bring a short account of what has changed, when it began, how it affects sleep and functioning, what you've tried, and whether you've noticed thoughts of self-harm.

    Check the professional before booking

    In India, verify that a clinical psychologist has appropriate Rehabilitation Council of India registration. For a psychiatrist, check medical registration through the relevant state medical council or the applicable MCI or NMC pathway.

    Titles can be confusing, and not every person offering “counselling” has the same training. Ask what qualification the provider holds, what registration applies, and whether they regularly work with depression.

    Questions that make the first session useful

    • Experience: “How do you usually assess and treat depression?”
    • Method: “Which therapy approach do you use, and how will we know whether it's helping?”
    • Frequency: “How often would you suggest sessions at the beginning?”
    • Coordination: “If you think I need medication, how do you refer to or work with a psychiatrist?”
    • Costs: “What are the fees, cancellation rules, and likely follow-up arrangements?”
    • Access: “Do you offer tele-consultation, and how do you handle urgent concerns?”

    A current therapist can refer you to a psychiatrist without ending therapy. Share consent for relevant information to be exchanged, especially medication history, symptom changes, risk concerns, and treatment goals.

    Urgent help matters more than provider preference. Active suicidal plans, recent self-harm, sudden personality change, hallucinations, delusions, severe confusion, or inability to care for basic needs require urgent psychiatric or emergency attention.

    Government hospital OPDs, medical colleges, private hospitals, tele-consultation platforms, and community organisations can all be starting points. If cost is a concern, ask about sliding-scale arrangements, public services, employer support, and insurance terms. A Bengaluru workplace survey found that only one in four people received mental-health support at work, according to the White Swan Foundation workplace mental-health survey, so don't assume your employer's programme is the only option or that support is automatically available.

    Supportive Takeaways for Moving Forward

    The psychologist-vs-psychiatrist decision becomes clearer when you ask three questions: How severe are the symptoms? How safe am I right now? What kind of help can I access consistently?

    For mild or moderate depression without urgent safety concerns, therapy with a psychologist is often a reasonable first step. A psychiatrist becomes more important when medication may be needed, symptoms are severe, a physical contributor is possible, previous treatment hasn't helped, or risk is increasing.

    Combination care isn't a sign that you've failed at therapy or that medication has “won”. It allows two professionals to work on different parts of the same problem. One may support medical stability while the other helps you rebuild routines, relationships, confidence, and coping skills.

    Progress rarely moves in a straight line. You may need to adjust the therapy approach, seek a second opinion, change professionals, add psychiatric care, or return to an earlier step. Finding a different provider when the fit isn't right is a practical part of care, not a personal failure.

    Concerns that deserve compassion

    Cost can make people delay care. Stigma can make them minimise symptoms. Family opinions may create pressure, and fear of medication may come from stories that don't match their own health needs.

    You don't have to settle every concern before asking for help. Write down your questions and ask the professional to explain benefits, risks, alternatives, monitoring, and what happens if the first plan doesn't suit you.

    Positive psychology belongs here too. Resilience, compassion, happiness, gratitude, emotional balance, and purpose aren't substitutes for depression treatment, but they can become meaningful parts of well-being as care progresses. Support can address workplace stress, anxiety, burnout, loneliness, relationship strain, and the habits that help you feel more connected to life.

    An infographic titled Supportive Takeaways for Moving Forward, outlining four key points for seeking mental healthcare.

    Assessments can help you describe patterns, but they're informational, not diagnostic. Use them to prepare for a conversation, not to decide on medication or label yourself.

    In the next 48 hours, choose one small action: list three symptoms and when they began, book an initial psychology session, contact a psychiatrist, or ask someone you trust to help make the call. You don't need to predict the entire journey. You only need to make the next safe, informed step.


    DeTalks helps you explore psychologists, therapists, and mental-health professionals by concern, including depression, anxiety, stress, and workplace well-being, while its assessments are intended to offer informational insight rather than diagnosis. Visit DeTalks to review suitable support options and take one practical step towards care.