
Tag: trauma therapy

  • What Is Trauma Therapy? a Plain Guide for Indian Readers

    What Is Trauma Therapy? a Plain Guide for Indian Readers

    Why does a low national trauma figure leave survivors wondering if their pain counts? Trauma therapy is structured psychological care for lasting trauma symptoms, and Indian estimates show why one size cannot fit everyone. Current PTSD in the general population is low, while rates after natural disasters run much higher.

    A national average is a rainfall map: it describes the region, not your street. In India, exposure varies by flood zone, conflict, road accidents, domestic abuse, and workplace harm. A low national estimate can make personal suffering feel statistically unlikely. It isn't. Many people steady themselves through support, time, and resilience. Others stay on high alert, avoid ordinary places, or feel numb long after the danger has passed. Therapy and counselling exist for that second group, and for anxiety, depression, and workplace stress beside trauma. LGBTQ+ survivors also need a therapist who won't treat identity as the problem. A screening result can point you toward help. It does not diagnose you.

    What Trauma Therapy Means in Plain Language

    Trauma therapy is structured psychological care for people affected by a traumatic event or by trauma symptoms that keep going long after it. Its three core goals are to process traumatic memories, reduce avoidance and hyperarousal, and restore safety plus daily functioning.

    Picture a smoke alarm that keeps ringing after the kitchen is clear. The alarm once protected you. It has not learned that the room is safe. Therapy does not erase the memory. It helps that alarm settle so you can cook, sleep, and leave the house without treating every trace of smoke as a new fire.

    Not every hard season produces trauma symptoms. Grief, exam pressure, and a bruising month at work can hurt without becoming trauma. Plenty of people recover through friends, rest, and their own resilience. When reactions stay stuck, counselling becomes more than a kind conversation.

    India's 2015–16 National Mental Health Survey, summarised by the Press Information Bureau, found that about 10.6% of adults were living with a diagnosable mental disorder, with a lifetime figure of 13.7%, roughly 14 in every 100 people. The same survey reported that 70%–92% of people with mental disorders did not receive proper treatment, because of limited awareness, stigma, and shortages of trained professionals. That is why therapy matters for anxiety, depression, workplace stress, and wider well-being, not only for trauma.

    How it differs from general counselling

    General counselling can steady mood, relationships, and daily stress. Trauma therapy targets trauma-linked symptoms in particular, such as intrusive memories and a body that will not stand down. Supportive counselling often sits beside that work rather than replacing it.

    If your reactions still run the day long after the event, ask whether they feel stuck, not whether you are "strong enough." A screening tool offers information. It is not a diagnosis.

    The Symptoms Trauma Therapy Is Built to Ease

    Trauma symptoms are the mind and body trying to protect you. That is why they feel so stubborn. They are not a character flaw, and they are not proof that you are broken.

    Five clusters show up again and again. Intrusive memories arrive as flashbacks, nightmares, or images you did not invite. Avoidance means skipping the bus, the relative, or the conversation that brushes the event. Hyperarousal is the jumpiness, the poor sleep, the short temper. Negative beliefs and mood can sound like shame, guilt, or numbness, including the thought "I am broken." Dissociation is the foggy, detached, or unreal feeling that makes the room seem far away.
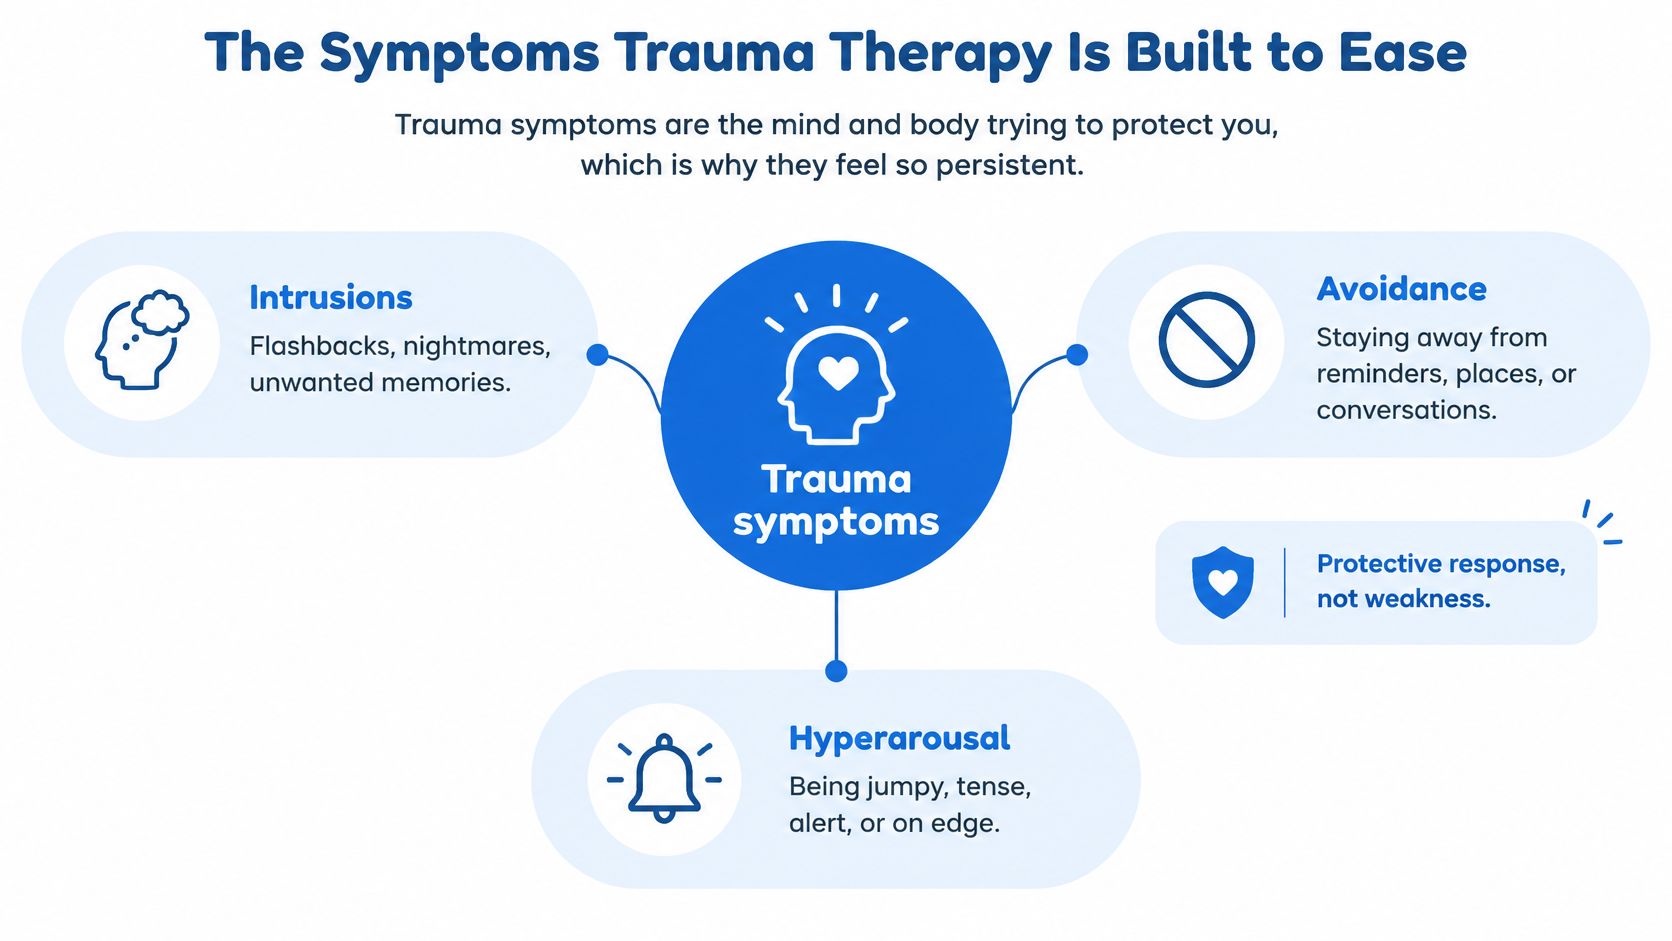
    An infographic showing the three main trauma symptoms that therapy aims to ease, including intrusions, avoidance, and hyperarousal.

    A commuter may refuse a familiar bus route after a road accident. A nurse may lie awake after a violent shift, even in a quiet flat. These are protective habits that overstayed.

    Symptom cluster What it can look like What trauma therapy targets
    Intrusive memories Flashbacks, nightmares, distressing images Processing the memory so it loses its grip
    Avoidance Skipping places, people or thoughts linked to the event Gradual, safe re-engagement with avoided situations
    Hyperarousal Constant alertness, startle responses, poor sleep Calming the body's threat response with skills and practice
    Negative beliefs and mood Shame, guilt, numbness, "I am broken" thinking Testing and reframing self-blame using evidence
    Dissociation Feeling detached, foggy or unreal Grounding and stabilisation before any trauma processing

    These patterns overlap with depression, anxiety, and burnout. A clinician should screen for all of them rather than assume one cause. When symptoms keep disrupting work, relationships, or sleep for several weeks or more, that is a reason to seek a professional assessment. The patterns here are for information only. They are not a diagnosis.

    If numbness and shame have lasted for years rather than weeks, a counseling perspective on complex trauma from Katy Teen & Family Counseling can help you tell a single overwhelming event from harm that stacked up over time.

    Main Types of Trauma Therapy and How They Differ

    No single method suits everyone. The better fit depends on the type of trauma, your symptoms, your safety, and what you are willing to try.

    Approach Core idea Often suited for
    EMDR Bilateral stimulation while recalling the memory Single-incident trauma and PTSD symptoms
    Trauma-focused CBT Identifying and reframing trauma-linked thoughts, with gradual exposure Adults and children with PTSD, shame and guilt
    Prolonged exposure Repeated, safe revisiting of memories and avoided situations Persistent avoidance after assault or accident
    Narrative exposure therapy Building a life-story timeline that includes multiple events Repeated or multiple traumas, including low-resource settings
    Somatic therapies Tracking body sensations and releasing stored activation Hyperarousal, numbness and body-based distress

    EMDR and trauma-focused CBT

    EMDR (eye movement desensitisation and reprocessing) pairs recall of a memory with bilateral stimulation, such as guided eye movements or tapping. The aim is to take the sting out of the memory so it sits in the past. It is often considered when there is a clearer incident and classic PTSD symptoms.

    Trauma-focused CBT helps you spot beliefs such as "it was my fault" and test them against what really happened. Gradual exposure is part of the work, always inside a plan you understand. A child version brings parents in, so the young person is not doing the hard part alone. Shame and guilt are common reasons clinicians reach for this approach with adults as well as children.

    Exposure, narrative work, and the body

    Prolonged exposure asks you to revisit the memory, and the situations you have been dodging, in a safe and repeated way. Avoidance shrinks when the body learns that the reminder is not the event. It is often used when avoidance after an assault or accident has taken over the week.

    Narrative exposure therapy lays events on a life-story timeline, including moments of strength, not only harm. It suits people with several or repeated traumas, and it has been used in low-resource settings where long specialist courses are hard to arrange.

    Somatic therapies track sensations such as a tight chest, numb hands, or a held breath, and help that activation settle. They are often combined with another method rather than used as the whole plan, especially when distress lives mainly in the body.

    A longer course is not a sign of failure. Reference ranges in treatment descriptions are often a few weeks to a few months, and your clinician sets the real length after assessment, based on symptoms, safety, and progress.

    EMDR, trauma-focused CBT, and prolonged exposure carry the strongest research support for PTSD in many treatment guidelines. Somatic approaches have a smaller evidence base and tend to work best alongside those methods. A clinician chooses by looking at symptoms, current risk, your preferences, and the therapist's training. You can ask why one method was picked, and you can say if the pace feels wrong.

    Who Benefits and When Trauma Therapy Helps Most

    Who benefits from trauma therapy? The honest answer is broader than many assume, and it depends far less on how tough you are than on what happened and what has remained unresolved since.

    A 2024 cross-sectional study in the Indian Journal of Psychological Medicine screened 600 flood victims in Kerala and found that 298 of them, or 49.7%, screened positive for post-traumatic stress disorder three months after the disaster, as the study abstract on PubMed reports. People with ordinarily strong coping skills were in that group. Resilience tends to mean a faster recovery, not an exemption from needing one.

    Set that beside the national picture. An analysis of India's National Mental Health Survey, readable in the full PMC article, interviewed 34,802 people and identified 64 with current PTSD, an estimated 0.2% of the general population. A national average behaves like average rainfall for a whole country: it says almost nothing about the district sitting under a cloudburst. Both figures are true at once because general surveys include many people who have never faced severe trauma, which pulls the number down. Survivors of disasters and of violence carry far heavier rates.

    Who often needs this kind of care

    • Disaster survivors: Floods, cyclones, and fires can leave sleep, startle, and grief tangled together.
    • People harmed by others: Violence, abuse, and road accidents often bring shame as well as fear.
    • Medical trauma survivors: A frightening procedure or a life-threatening illness can leave the body braced for the next alarm.
    • First responders and healthcare workers: Repeated exposure at work can sit under a calm professional face.
    • Employees facing harassment: Workplace stress may ease with counselling, coaching, and clearer boundaries. Flashbacks and avoidance need trauma-focused care, not only a workload tweak.

    Screening numbers tell you how common a problem is. They do not tell you whether your own sleep, concentration, or relationships have reached the point where help would change the outcome. That judgement belongs inside an assessment.

    Identity, safety, and growth

    For LGBTQ+ people in India, discrimination, family rejection, concealment, and previous harm in clinics can shape the trauma itself. A 2026 narrative review of India's LGBTQ+ community, published by Springer, links stigma, homophobia, microaggressions, and re-traumatisation in healthcare with complex PTSD, and notes that community and government responses remain limited. Identity-affirming, consent-based care means you control what you disclose, and you are not pushed toward family members who may be unsafe.

    Distress and growth can exist together. Therapy can strengthen compassion, emotional intelligence, and resilience without pretending the harm was useful. If symptoms outlast the first few weeks, or they block daily life, that is reason enough to seek help.

    How Assessment and Treatment Pathways Unfold

    Care works better as a sequence than as a single brave conversation. Each stage answers a different question, and skipping ahead can leave someone flooded.
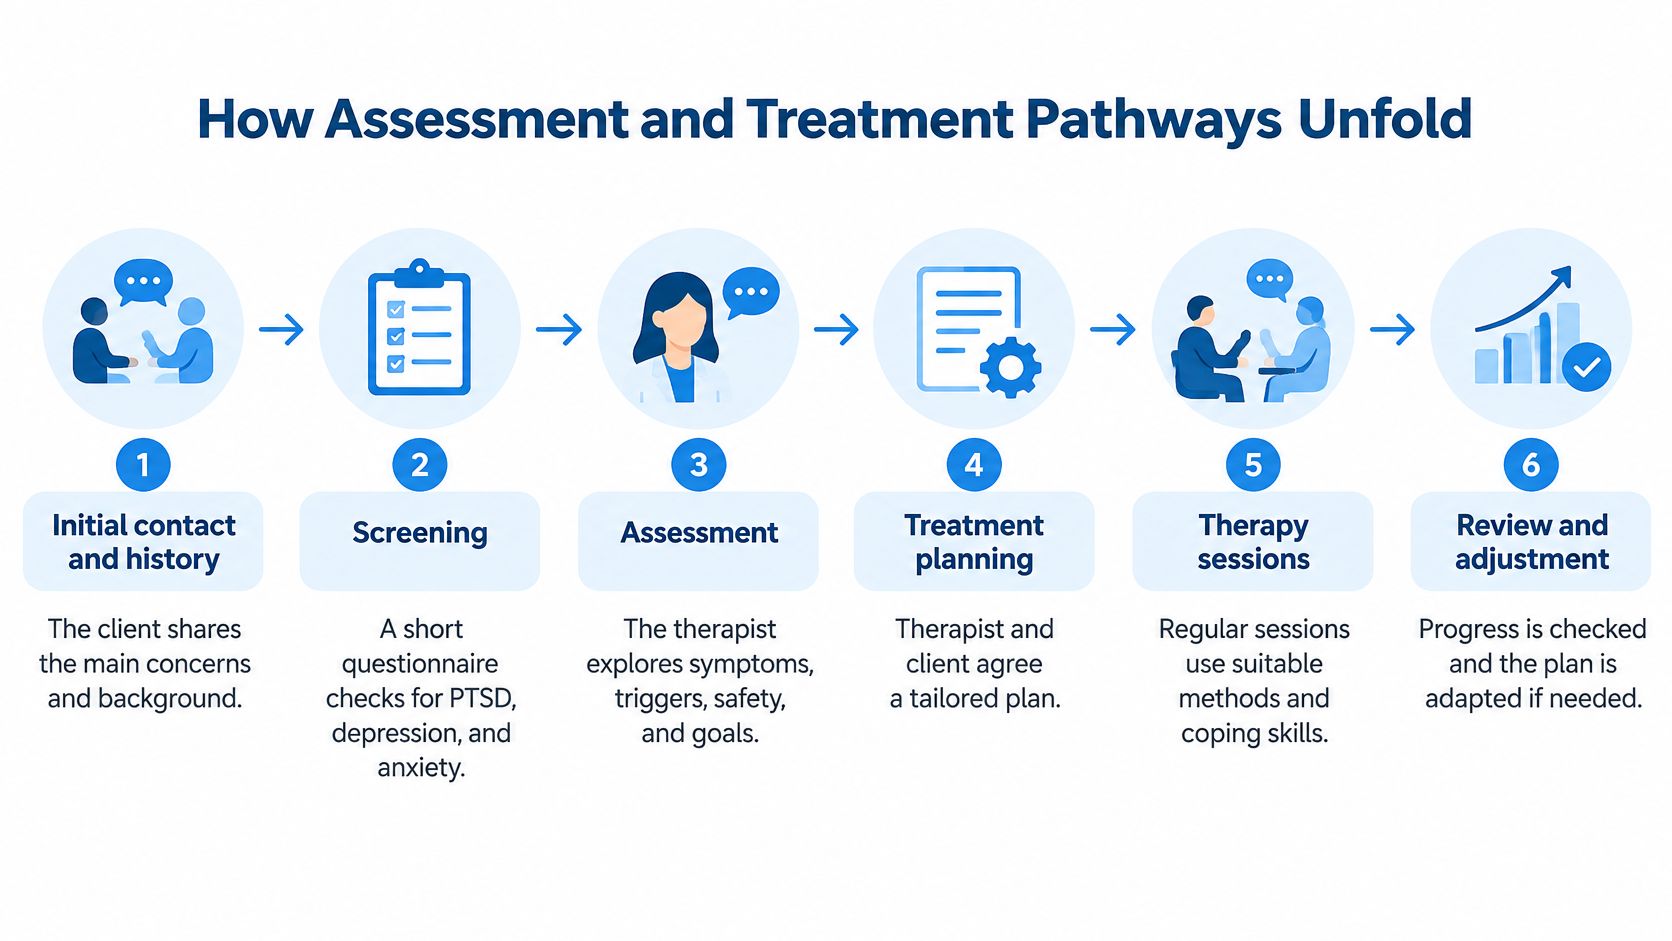
    A flowchart showing six sequential steps of a therapy process from initial contact to review and adjustment.

    1. Initial contact and history. You share the main concerns and a sketch of your background, so the clinician knows what brought you in before anyone names a method.
    2. Screening. A short questionnaire checks for PTSD, depression, anxiety, substance use, suicidal thoughts, and dissociation, because these problems travel together.
    3. Clinical assessment. A qualified professional reviews the screening and the history to form a clinical picture. Screening is informational. It does not replace this step.
    4. Safety and stabilisation planning. Sleep, grounding, a crisis plan, and any medical needs come first, so later work has a floor under it.
    5. Trauma-focused treatment. The chosen method is delivered at a pace you can manage, with room to pause.
    6. Consolidation and relapse prevention. Gains are reviewed and a plan for setbacks is built, because a bad week does not erase the work.

    Where people enter

    A GP or psychiatrist can handle referral and medical needs. A clinical psychologist often provides the trauma-focused therapy. Some people self-refer to a counsellor. The door matters less than whether the next person can assess risk and match the method.

    A five-year review of 59,769 psychiatric outpatients, reported in PMC, found only 131 adults with a recorded PTSD diagnosis, and among those receiving psychological intervention, just 18% received evidence-based trauma-focused treatment. In that group the trauma was interpersonal in 75.2% of cases. Those figures are a reason to ask, early, whether the plan is trauma-focused.

    Public routes exist alongside private care. As of 31 January 2025, India's Ministry of Women and Child Development reported 812 operational One Stop Centres that had assisted more than 1.08 million women, and the government's trauma-informed Project Stree Manoraksha uses these centres to strengthen mental-health care for survivors of gender-based violence, according to the Press Information Bureau.

    A pathway is a guide, not a fixed timetable. Stabilisation may need longer if you are still unsafe or emotions swing hard. Premature exposure can raise distress and dropout.

    Safety Steps and Crisis Support to Know Now

    Separate danger from distress before you pick a tool. Danger means thoughts of harming yourself or others, violence at home, or a medical emergency. Those need immediate help, not a breathing exercise alone. Distress can be severe and still be something you can ride out with skills and a person on the phone.

    Situation What to do now
    Thoughts of harming yourself or others Call 112 or go to the nearest emergency department, and stay with someone until help arrives
    Feeling unsafe at home or facing violence Leave if you safely can, call 112, and use Tele-MANAS on 14416 for free multilingual support
    Overwhelming distress without immediate danger Use a grounding step or slow breathing, then call 14416 or your therapist
    Substance use alongside trauma symptoms Seek urgent medical advice on withdrawal before starting trauma processing, and tell any therapist about current use
    Dissociation or feeling unreal for hours Use grounding steps now and contact a clinician the same day; seek emergency care if it does not ease or you feel unable to keep yourself safe

    Two steps you can use in the moment

    For panic or dissociation, try 5-4-3-2-1. Name five things you can see, four you can touch, three you can hear, two you can smell, and one you can taste. Then slow your breathing with a longer exhale than inhale. The longer out-breath tells the body the emergency is easing.

    Write a simple safety plan while you are calmer. List warning signs, coping steps, people to contact, professional numbers, and what a safer room looks like. Keep 112 and Tele-MANAS (14416) on that page. As of 7 February 2025, India's Ministry of Health and Family Welfare reported that Tele-MANAS had handled 1,827,951 calls since its 2022 launch, a scale of demand noted by the Press Information Bureau.

    Online therapy helps many people with anxiety, low mood, and ongoing trauma symptoms. It is not enough for acute suicidality or severe alcohol or drug withdrawal, where in-person or emergency care comes first.

    If you are supporting someone, ask directly whether they are thinking of suicide. Stay with them, and help them reach emergency care. Do not leave them alone to "sleep it off."

    What Happens in Your First Few Sessions

    Say Meera is 34, a teacher who has avoided driving since a road accident. She is capable at work and frightened in a car park. That mix is common.

    A female therapist listens attentively as her client discusses mental health during a professional therapy session.

    In the first session the therapist takes a history, agrees goals, explains why this method might help, and checks consent. Meera learns she can skip a question. The point of session one is a map, not a full retelling of the crash.

    Skills before the hard memories

    The next few sessions focus on stabilisation. Meera practises breathing and grounding, tidies a sleep routine, and hears, in plain language, how trauma keeps the body on duty. This is not delay. Processing a memory before she can come back to the room would only scare her off.

    In the middle phase the chosen method starts at a pace she can manage. She can pause, set limits, and decide what to disclose. Between sessions she tracks triggers and uses one grounding exercise. Homework stays short on purpose.

    A clear walk-through of early sessions, including why therapists slow down, sits in this short film.

    Later, the therapist reviews progress with simple measures. Meera notices the memory feels less sharp. Setbacks and emotional spikes still happen, and they are named rather than treated as failure. Progress is usually uneven, not a straight line.

    You can ask about credentials, stop at any time, and expect each step to be explained. Bring a list of concerns, current medications, and emergency contacts to the first meeting.

    Choosing a Qualified Provider and Taking the Next Step

    A safe therapist answers direct questions about training, methods, and limits. Use a short checklist before you book.

    An infographic titled Choosing a Qualified Provider and Taking the Next Step, outlining five steps for finding mental health professionals.

    • Check registration. Clinical psychologists should be registered with the Rehabilitation Council of India.
    • Know who can prescribe. Psychiatrists are medical doctors. Counsellors should hold recognised training, and they do not replace medical care.
    • Look for trauma-specific training. Ask about EMDR, trauma-focused CBT, or prolonged exposure, and about experience with your kind of event.
    • Ask about language and respect. Confirm the therapist works in your preferred language, and, if you are LGBTQ+, whether the care is identity-affirming.
    • Confirm consent and practicalities. You should hear about pacing, your right to stop, fees, session format, and the emergency plan.

    Access remains uneven across India. The Ministry of Health and Family Welfare reports that India has about 0.75 psychiatrists per 100,000 people, against a WHO benchmark of at least 3 per 100,000, and that Tele-MANAS offers support in 20 Indian languages. As of 19 March 2025, the Ministry reported that 36 states and union territories had set up 53 Tele-MANAS cells, according to the Press Information Bureau. Language-matched help may be closer than a big-city clinic. If substance use is in the picture, ask whether trauma care can be sequenced with addiction treatment.

    For a plain-language guide to the principles a trauma-informed therapist should be able to explain, see evidence-informed therapy for people experiencing trauma.

    DeTalks brings psychologists, therapists, and counsellors into one directory so you can compare profiles and book sessions. The platform's assessments and screening tools give informational insights, not a diagnosis, and curated self-help can sit beside therapy. Resilience and compassion are practices you keep, not a cure someone hands you.

    Three small steps are enough for this week. Take one screening tool, shortlist two providers, and book one consultation.

    If trauma symptoms, anxiety, or low mood are crowding out your days, DeTalks can help you compare qualified therapists across India and book counselling that fits trauma-focused care. You can also use informational screening tools and self-help while you decide on next steps for your well-being. Visit DeTalks when you are ready to take one clear step.

  • Trauma Informed Therapist: A Practical Guide to Healing

    Trauma Informed Therapist: A Practical Guide to Healing

    Sunday night can make a difficult week feel even louder. Reena, a 32-year-old marketing professional in Bengaluru, lies awake replaying a critical email, a heated call with her mother, and the sleepless night that followed. She keeps wondering, “Why am I still so on edge?”

    A trauma informed therapist would not assume that Reena is overreacting or ask her to reveal her most painful memory immediately. Instead, the therapist would become curious about what her mind and body are communicating, while helping her feel safe enough to explore it.

    Trauma-informed therapy can support people facing stress, anxiety, depression, burnout, grief, relationship difficulties, workplace stress, and emotional numbness. It isn't limited to people with a formal diagnosis of post-traumatic stress disorder, and it doesn't require you to describe every detail of what happened.

    India's need for accessible, sensitive mental-health care is substantial. The National Mental Health Survey 2015–16 found that 10.6% of Indian adults had a current mental disorder, 13.7% had experienced one during their lifetime, and the treatment gap was around 85%. A separate national analysis estimated that 197.3 million people in India were affected by mental disorders in 2017, with mental disorders' share of the total disease burden rising from 2.5% in 1990 to 4.7% in 2017 (national burden summary).

    The right therapist won't rush you towards a dramatic breakthrough. They'll help you build safety, choice, self-understanding, resilience, and compassion through a pace you can tolerate.

    What Trauma Informed Therapy Feels Like

    A safer way to understand distress

    Reena may enter therapy believing her problem is “overthinking”. Anxiety before meetings, tight shoulders, poor sleep, or a strong reaction to criticism can carry information about earlier experiences, repeated stress, or a history she has never called trauma.

    The therapist does not decide what happened to her. Trauma-informed care is a way of delivering therapy, not a single treatment method. It asks, “What might have happened to you, and what could help you feel safer now?” This shifts attention from blaming a reaction to understanding what may be shaping it.

    Before discussing anything sensitive, the therapist may ask what Reena wants from the session. They can explain why a question matters and offer choices. Reena can pause, change the subject, or say no.

    Less digging, more steadiness

    Many people worry that trauma therapy means describing their worst experience in detail. A skilled trauma informed therapist understands that moving too quickly can increase fear, shame, shutdown, or emotional flooding.

    Early sessions may focus on sleep, grounding, boundaries, emotional regulation, or recognising signs that stress is building. The therapist and client then decide together whether deeper processing fits the client's needs and when it might be appropriate.

    A practical rule: You shouldn't have to earn safety by disclosing more than you're ready to share.

    India's PTSD evidence also supports careful assessment that considers local context. A systematic review of Indian studies found that PTSD prevalence varied by trauma type, averaging 31% after natural disasters, 28% after abuse, and 16.4% after man-made accidents. The review described outcomes ranging from 89% among survivors assessed three months after the 1999 Odisha cyclone to 0.01% in one tsunami-survivor cohort. These differences show why trauma type, timing, and assessment methods matter.

    For Reena, healing might start with noticing how a critical email brings back an old sense of danger. A therapist who works this way does not force a journey into the past. They stay beside the client while she builds enough safety and confidence to understand what is happening in the present.

    When reviewing a directory such as DeTalks, look beyond a therapist's label. Check whether their profile explains how they discuss consent, pacing, safety, and client choice. Those details offer a practical first indication of whether trauma-informed care shapes their work, rather than serving only as a name.

    The Core Principles Behind Trauma Informed Care

    Trauma-informed care is commonly described through a framework developed by the Substance Abuse and Mental Health Services Administration. A trauma-informed therapist works like a guide who shows you the terrain without deciding your destination. They bring clinical knowledge, while you retain a say in the pace, focus, and direction of therapy.

    Six principles in everyday language

    1. Safety includes physical, emotional, and psychological comfort. The room, online setting, language, and pace should reduce avoidable fear. Before discussing something difficult, the therapist may ask whether you feel ready to continue.

    2. Trustworthiness and transparency mean explaining what will happen. Clear information about confidentiality, fees, cancellations, assessments, and treatment choices reduces uncertainty. The therapist might also explain why they are asking a question, allowing trust to develop through clarity.

    3. Peer support recognises how connection can ease isolation. Peer groups, survivor communities, and shared support may help when they are appropriate and safely facilitated. A therapist asks whether this kind of support suits you instead of making assumptions.

    4. Collaboration and mutuality make therapy shared work. The therapist contributes expertise, while your observations shape the plan. They may offer an option, explain its purpose, and invite your view before deciding how to proceed.

    5. Agency, voice, and choice help return control to the client. You can decide what to discuss, which goals matter, and whether a technique feels acceptable. For example, a therapist may offer two grounding exercises and let you choose between them.

    6. Cultural, historical, and gender awareness recognises that identity affects safety and meaning. Religion, caste, language, sexuality, disability, gender, family structure, migration, and collective or historical harm may shape distress. A culturally responsive therapist asks how your background influences your experience rather than forcing it into an imported assumption.

    An infographic detailing the six core principles of trauma-informed care for patients and practitioners.

    These principles do not promise constant comfort. Meaningful work can bring sadness, anger, or uncertainty. The difference is that discomfort is discussed openly, paced carefully, and never treated as proof that the therapist knows best.

    India's National Disaster Management Authority manual describes trauma-informed care through physical, psychological, and emotional safety, shared decision-making, collaboration, and recovery-oriented care. It also places cultural competence and person-centred goal setting within responsible care.

    When checking a therapist on DeTalks, look past the label. Read for practical details about consent, pacing, safety, and client choice. Those details can help you judge whether trauma-informed care shapes the therapist's practice, rather than appearing only in a profile description.

    Approaches a Trauma Informed Therapist May Use

    A trauma informed therapist may use several approaches, depending on your concerns, stability, preferences, and goals. The label matters less than the reasoning behind the choice. A responsible clinician will explain the method, ask for consent, and adjust if you feel overwhelmed.

    Matching the method to the person

    Eye Movement Desensitisation and Reprocessing, or EMDR, uses structured memory processing with bilateral stimulation, such as guided eye movements or tapping. It may be considered when distressing memories remain vivid, intrusive, or emotionally charged. You shouldn't be expected to begin this work before you have enough grounding and a clear understanding of the process.

    Somatic and body-based work pays attention to physical experiences such as muscle tension, freezing, restlessness, shallow breathing, or feeling disconnected from the body. Sensorimotor Psychotherapy and yoga-informed therapy may help a client notice bodily signals and practise regulation without requiring immediate detailed storytelling.

    Trauma-sensitive CBT combines cognitive and behavioural tools with awareness of how trauma can affect beliefs, trust, attention, and threat perception. The therapist may help you examine thoughts such as “I'm never safe” or “Everything is my fault”, while avoiding a simplistic demand to think positively.

    Internal Family Systems, or IFS, uses the idea of inner “parts” to explore experiences such as an inner critic, a protective part, or a younger wounded part. For some clients, this language feels gentler than treating conflicting thoughts as evidence that something is wrong with them.

    Indian clinicians may blend approaches rather than follow one model rigidly. The National Disaster Management Guidelines identify the value of training in trauma-focused psychotherapies, disaster-specific reactions, cultural expressions of distress and grief, ethical practice, and standardised screening tools.

    A quick comparison

    Approach Main Focus Best Suited For
    EMDR Structured processing of distressing memories People who want a guided approach to memories that still feel emotionally present
    Somatic work Body sensations, tension, shutdown, and regulation People whose trauma shows up strongly through physical symptoms or disconnection
    Trauma-sensitive CBT Beliefs, coping patterns, and present-day behaviour People dealing with anxiety, guilt, avoidance, or fearful interpretations
    IFS Understanding protective and wounded inner parts People who experience strong inner conflict, self-criticism, or emotional complexity

    No modality is automatically right for everyone. The strongest sign of good practice is a collaborative explanation, informed consent, and willingness to slow down.

    What Good Trauma Informed Care Looks Like in a Session

    A trauma informed session often begins with practical choices. The therapist welcomes the client, offers water, explains how the meeting will work, and says they may pause, redirect, or skip a topic. This opening establishes that consent continues throughout the conversation, rather than ending once the session starts.

    The therapist asks what brought the client in and what would make the meeting useful. They listen to the client's words while also noticing changes in breathing, posture, eye movement, and energy. These observations guide gentle curiosity, not instant conclusions.

    Small behaviours reveal the approach

    Suppose a client describes a difficult family interaction. Their eyes move towards the door, breathing becomes shallow, and one leg begins bouncing. A careful therapist may name the change, ask whether the client has noticed it, and offer choices: pause, use a grounding exercise, or continue with a less intense topic.

    Grounding can be ordinary and practical. The therapist might suggest slower breathing, noticing the chair's support, naming objects in the room, or feeling both feet on the floor. These tools do not erase emotion. They help the client return to a level of alertness where thinking and choice are possible.

    A professional trauma informed therapist welcoming a new client into her warm and inviting office space.

    Near the end, the therapist checks how the client is feeling and discusses what may help after the session. They might summarise what they heard, ask whether that summary feels accurate, and agree on a manageable next step.

    What rushed care can feel like

    Rushed care may bring invasive questions before trust has developed, immediate advice, or pressure to label the experience. The therapist may speak more than the client, dismiss physical responses, or interpret distress as resistance.

    A strong session has a clear rhythm: the client understands what is happening, has room to influence the pace, and can ask for clarification. Difficult material may still arise, yet the therapist explains its purpose and responds when the client becomes overwhelmed. These details offer a practical way to assess a therapist's profile on a directory such as DeTalks. Look for evidence of how they work, not only the phrase trauma informed therapist in a listing.

    Questions to Ask and Red Flags to Notice

    You don't need to sound clinical during a discovery call. A few direct questions can help you understand whether a therapist's training and style match what you need.

    Training and experience

    • Ask about trauma-specific training: “What trauma-specific training have you completed?” This helps distinguish focused education from a general statement on a profile.
    • Ask about relevant experience: “Have you worked with concerns such as anxiety, grief, abuse, workplace stress, or dissociation?” A therapist should answer within appropriate confidentiality boundaries.
    • Ask about cultural responsiveness: “How do you adapt therapy for language, family, religious, gender, or identity-related concerns?” Your context should have room in the work.

    Session structure

    • Ask about pacing: “How do you decide when to discuss difficult memories?” A trauma informed therapist should describe preparation, stabilisation, and ongoing check-ins.
    • Ask about overwhelm: “What do you do if I become distressed or disconnected during a session?” The answer should include practical ways to pause and regulate.
    • Ask about methods: “Which approaches might you use, and how would we decide?” You deserve an explanation rather than a technique imposed without discussion.

    Collaboration and logistics

    • Ask about shared decisions: “How would you involve me in deciding what we work on?” This reveals whether the therapist sees you as an active participant.
    • Ask about confidentiality: Clarify its boundaries, particularly for online counselling and any communication outside sessions.
    • Ask about practical policies: Discuss fees, rescheduling, session format, availability, and what happens if the therapist believes you need another level of care.

    An infographic titled Questions to Ask a Potential Therapist, organized into categories of training, dynamics, and logistics.

    Red flags deserve equal attention:

    • Dismissed responses: Calling your reactions dramatic or irrational can increase shame instead of building understanding.
    • Pressure to disclose: Insisting on detailed memories before trust and stability are established ignores your autonomy.
    • Guaranteed cures: No ethical therapist can promise a fixed outcome or timeline.
    • One method for everyone: A therapist who pushes one modality without considering your needs may not be a good fit.
    • Missing informed consent: You should understand what will happen and have a real opportunity to agree, decline, or pause.

    During a discovery call, notice how your questions are received. The answer matters, but the therapist's openness matters too.

    Finding and Booking the Right Therapist in India

    When you are already overwhelmed, finding the right therapist should not require another layer of research. Start with the concern you can name, such as anxiety, grief, past abuse, depression, burnout, sleep problems, or workplace stress. You do not need the perfect clinical label before contacting someone.

    Use filters as a starting point

    On a directory such as DeTalks, search for your main concern, then look for terms such as trauma informed, EMDR, somatic work, or IFS. These labels are useful search prompts, not proof of how a therapist works. Verification comes from the therapist's answers, pace, and willingness to explain their process.

    Read each profile for training, relevant experience, languages, location, and session format. An Indian client may want Hindi, Bengali, Tamil, Marathi, or another language. You may also want someone familiar with a particular family, religious, gender, sexuality, disability, or workplace context.

    Screenshot from https://detalks.example.com/therapist-listing

    Send a short message before booking. Name the concern you want help with, say whether you prefer online or in-person sessions, and ask how the therapist applies trauma-informed care in practice. You might ask how they respond when a client becomes overwhelmed, or how they decide whether to slow down. A practical guide to websites for therapists can help you understand how professional profiles and online practice information are presented.

    Keep the first contact low pressure

    Prepare two or three questions for a trial or assessment call. Ask what the first sessions usually involve and how you will participate in deciding the treatment plan. Notice whether the therapist answers clearly, welcomes questions, and leaves room for you to pause or reconsider.

    Check fees, confidentiality, rescheduling policies, and whether sessions are online or in person in your city. Clear arrangements support a steadier start because uncertainty about access, privacy, or continuity can make therapy harder to begin.

    Any assessment offered through DeTalks should be understood as informational, not diagnostic. A screening tool can help you reflect on symptoms, well-being, resilience, or possible areas for support. It does not replace a clinical evaluation by a qualified professional.

    The first therapist you contact may not be the right match. You can choose someone else if the communication style, identity awareness, pace, or approach does not suit you. One conversation is enough to learn more and decide what feels safe to try next.

    Supportive Takeaways for Your Healing Journey

    A trauma informed therapist doesn't take control of your healing. They walk alongside you, helping you notice patterns, strengthen emotional regulation, and make choices with more confidence. The work may include difficult memories, but it can also include happiness, compassion, gratitude, purpose, connection, and pride in small acts of resilience.

    Healing rarely follows a straight line. A week of better sleep may be followed by a difficult day. Feeling anxious again doesn't erase the progress you made. It may show that your mind and body need more support, rest, boundaries, or practice.

    India's mental-health burden makes gentle, accessible engagement especially important. The National Mental Health Survey summary reported a treatment gap ranging from 70% to 92%, which means many people who could benefit from therapy or counselling still don't receive it. Reaching out can therefore be practical self-care, not a sign of weakness.

    Work can also carry a heavy emotional load. A 2024 review of mental health among Indian employees reported 29% with moderate-to-severe signs of depression, 55% with moderate-to-severe signs of anxiety, and 78% with moderate-to-high stress. Those figures support taking workplace stress and burnout seriously, while remembering that such assessments are informational and not diagnostic.

    Let progress be manageable

    You might begin by writing down what you want from therapy. You might practise sensory grounding, speak to a trusted person, or book a discovery call without committing to ongoing sessions. Each action can strengthen your sense of voice and choice.

    Self-compassion doesn't mean ignoring responsibility. It means responding to difficult days with the same patience you might offer someone you care about. Resilience grows through repeated experiences of safety, support, reflection, and repair.

    Seeking support is an act of courage, even when you're unsure what to say.

    Assessments and self-check-ins can offer useful language for your experience, but they cannot diagnose you. A qualified mental-health professional can help you understand the broader picture and decide whether therapy, counselling, coaching, psychiatric care, self-help, or another form of support fits your situation.

    A discovery call or trial session is a reasonable first move. You're allowed to ask questions, honour your pace, change therapists, and take breaks when needed. Sustained support, patience, curiosity, and compassion can become steady companions as you build a life with greater safety and well-being.


    DeTalks offers a directory where you can browse psychologists, therapists, and counsellors by concerns, specialisations, and support needs, along with informational psychological assessments. Visit DeTalks to explore trauma informed care options and take one practical step towards support that respects your pace, identity, and goals.

  • Narcissistic Abuse Recovery: A Guide to Healing and Rebirth

    Narcissistic Abuse Recovery: A Guide to Healing and Rebirth

    You may be reading this late at night, replaying conversations and wondering how someone who said they loved you could also leave you so confused. You might feel anxious, flat, guilty, restless, or unable to trust your own memory. That reaction makes sense.

    Many people coming out of this kind of relationship don't first say, “I was abused.” They say, “I don't feel like myself anymore.” They notice stress in their body, anxiety in ordinary moments, trouble sleeping, low mood, workplace stress that suddenly feels impossible, or a constant fear of getting things wrong.

    Recovery begins there. Not with forcing yourself to “move on,” but with gently recognising that something harmful happened, and that your mind and body are trying to protect you. With the right support, therapy, counselling, and steady self-care can help you rebuild well-being, resilience, and a more compassionate relationship with yourself.

    Understanding the Aftermath of Narcissistic Abuse

    A common first sign is confusion. You may know something felt wrong, yet still hear an inner voice asking if you were too sensitive, too emotional, or too demanding. That self-doubt is often one of the deepest wounds.

    Take a familiar example. A woman leaves a relationship after months or years of criticism, blame, and emotional whiplash. Her phone is finally quiet, but she feels worse before she feels better. She checks old messages, questions her own judgement, struggles to focus at work, and wonders why relief hasn't arrived.

    A contemplative woman sitting on a chair looking out a window during narcissistic abuse recovery process.

    What this kind of harm often feels like

    Narcissistic abuse recovery isn't only about getting over a breakup or conflict. It often involves healing from repeated experiences that made you question your reality, minimise your needs, and stay focused on the other person's moods instead of your own well-being.

    You may notice:

    • Mental fog: forgetting details, second-guessing simple decisions, losing confidence in your own memory
    • Body stress: headaches, muscle tension, shallow breathing, poor sleep, exhaustion
    • Emotional swings: anxiety, sadness, numbness, anger, guilt, or periods that feel like depression
    • Social withdrawal: pulling back from friends, family, or activities you once enjoyed
    • Work strain: lower concentration, fear of criticism, burnout, or trouble managing workplace stress

    You don't need a perfect label for what happened before you deserve support.

    In India, many survivors also carry extra pressure from family expectations, silence around mental health, and the belief that private suffering should stay private. That can make recovery feel lonely, even when the damage is very real.

    Why early support matters

    Research involving 500 individuals in India highlights a critical risk. Victims who don't regain emotional or practical resources within the first year face a statistically significant delay in their recovery, which underscores the need for expert support to address the silent scars of manipulation and trauma and help prevent long-term psychological deterioration, as noted in this India-based survey research on recovery delay.

    If some of the harm also happened online, such as public shaming, threats, harassment, or reputation attacks, practical guidance on digital safety can help you feel less overwhelmed. This reputation management cyberbullying guide offers useful context for adults dealing with online psychological harm.

    A gentle but important reminder

    Self-checklists can help you organise your thoughts, but they are informational, not diagnostic. Only a qualified mental health professional can assess anxiety, depression, trauma-related symptoms, or other concerns in a clinical way.

    Healing doesn't mean pretending you're fine. It means learning to feel safe enough to return to yourself.

    Your First Practical Steps Toward Safety

    The first task isn't insight. It's safety.

    When someone has repeatedly pulled you into conflict, guilt, fear, or confusion, your nervous system often stays on alert. Clear boundaries help lower that alarm so your mind can begin to settle.

    A simple visual checklist can help when everything feels scattered.

    An infographic titled Immediate Steps for Safety outlining five steps for beginning recovery from abuse.

    Start with the strongest boundary you can safely keep

    Evidence-based recovery guidance identifies No Contact as the gold standard in narcissistic abuse recovery. That means no calls, no texts, no checking social media, no asking mutual friends for updates, and no replying to baiting messages.

    When full separation isn't possible, Grey Rock can help. This means being brief, neutral, and uninteresting. You don't explain, defend, or open emotional doors.

    Here's what that can look like:

    1. No Contact message
      “I won't be continuing contact. Please don't call or message me again.”
      Then block, mute, and remove easy access points if it's safe to do so.

    2. Grey Rock reply in a shared responsibility situation
      “I'll be there at 5 pm.”
      That's it. No emotional content. No argument. No invitation.

    3. Boundary with a mutual friend
      “I'm not discussing that relationship right now. I'd value your support in keeping some distance from updates.”

    Practical rule: A boundary is only real if you follow it with an action.

    Five actions that reduce immediate chaos

    You don't need to do everything today. Pick one or two steps and repeat them.

    • Secure your devices: change passwords, review privacy settings, and log out of shared accounts if relevant.
    • Reduce exposure: archive old chats, mute triggering contacts, and remove reminders that keep pulling you back into distress.
    • Tell one safe person: choose someone calm and trustworthy, and say clearly what kind of support you need.
    • Build a regulation routine: drink water, eat regularly, sleep when you can, and use simple grounding practices like slow breathing or a short walk.
    • Keep private notes if needed: if there are legal, custody, workplace, or family concerns, a private record may help you stay organised.

    A short video can also make these first steps easier to absorb when your concentration is low.

    When safety is complicated

    Sometimes the abuser is a spouse, parent, boss, or co-parent. Sometimes you live in the same home. Sometimes cultural pressure makes distance feel impossible.

    In those cases, aim for protective distance, not perfect freedom. Sit near supportive people when possible. Keep financial and identity documents accessible. Limit private emotional conversations. Rehearse neutral exits such as, “I'm not discussing this now,” or, “I need to leave this conversation.”

    Safety also includes emotional safety. If your stress, anxiety, panic, or low mood are getting worse, reach out for therapy or counselling sooner rather than later. You don't have to prove that it was “bad enough” before you ask for help.

    Healing the Wounds with Professional Therapy

    Once immediate safety is steadier, therapy can help you make sense of what happened without forcing you to relive it all at once. Good trauma-informed counselling doesn't rush you. It creates structure, choice, and a pace your body can tolerate.

    Many survivors feel relieved when recovery stops feeling random. There is a recognised path.

    A four-stage flowchart illustrating the process of narcissistic abuse recovery from stabilization to finding personal purpose.

    The four-stage recovery path

    A clinically validated model describes narcissistic abuse recovery as a four-stage path: (1) Establishing Safety, (2) Grief Processing, (3) Somatic Integration, and (4) Reconnection. It also notes that therapies such as EMDR and Trauma-Focused CBT are highly effective, while neglecting any stage can extend recovery timelines from one year to over five years, according to this four-stage recovery overview.

    That framework matters because many people try to skip ahead. They want confidence before safety, joy before grief, or trust before the body feels calm enough to receive it. Therapy helps place these pieces in the right order.

    What different therapies may help with

    The names can sound technical, so it helps to translate them into plain language.

    Therapy approach In simple terms Often helps with
    Trauma-Focused CBT noticing harmful thought loops and replacing them with steadier, more accurate ones self-blame, anxiety, shame, depression
    EMDR processing distressing memories so they feel less overwhelming in the present intrusive memories, body alarm, emotional flooding
    IFS understanding different “parts” of you, such as the fearful part, the people-pleasing part, or the angry part inner conflict, self-criticism, identity confusion
    Somatic work paying attention to what the body is holding and helping it release stored stress chronic tension, shutdown, restlessness, hypervigilance

    Healing often becomes easier when you stop asking, “Why am I still reacting like this?” and start asking, “What is my mind and body trying to protect me from?”

    Therapy is not about proving your pain

    A good therapist won't ask you to defend your story like a courtroom witness. They'll help you notice patterns, rebuild self-trust, and strengthen resilience in daily life.

    That may include grief work for the relationship you hoped for, stress management skills for workplace stress, support for anxiety or depression, and gentle exercises that restore self-compassion. If writing helps you process your story, this guide to healing and storytelling may offer a grounded way to think about personal narrative without forcing disclosure before you're ready.

    If you use online assessments while looking for support, keep one principle in mind. Assessments can offer insight and direction, but they are informational, not diagnostic. A qualified clinician is still the right person to interpret symptoms in context.

    Rebuilding Your Identity and Self-Esteem

    After prolonged criticism or control, many people don't just lose confidence. They lose familiarity with themselves. You may know your role in other people's lives very well, yet feel unsure about your own preferences, values, or voice.

    That's why rebuilding identity is not a luxury. It's part of healing.

    Start small enough to succeed

    You don't need a dramatic reinvention. You need repeated experiences of hearing yourself and responding with care.

    Try this for one week:

    • Choose one thing without outsourcing it: what to wear, what to eat, what music to play, where to sit in a room
    • Write one true sentence daily: “I felt tired today.” “I handled that call well.” “I don't like being spoken to that way.”
    • Notice body signals: tension, relief, heaviness, ease. Your body often reacts before your mind finds words.

    These tiny acts build self-trust. Self-esteem grows when your actions tell you, again and again, “My experience matters.”

    Work with the inner critic

    Many survivors carry the abuser's voice inside their own head. It may sound like harsh self-correction, guilt for resting, or panic after making ordinary mistakes.

    A helpful exercise is to separate the voice from the truth.

    Inner critic says Grounded response
    “You're overreacting.” “My feelings are information.”
    “You always ruin things.” “I made a mistake. That doesn't define me.”
    “No one will believe you.” “I don't need everyone's approval to honour my experience.”
    “You should be over this by now.” “Healing takes time and repetition.”

    This isn't fake positivity. It's accurate, compassionate thinking.

    Try speaking to yourself the way you'd speak to a close friend who is exhausted, anxious, and trying hard to heal.

    Rebuild a life, not just a defence

    Narcissistic abuse recovery becomes more stable when your life starts filling with your own values again. That includes pleasure, rest, meaning, and connection.

    A few practical areas to reclaim:

    • Relationships: spend more time with people who are steady, respectful, and not hungry for drama.
    • Work: if workplace stress has become intense, set clearer limits on after-hours access, overexplaining, or taking on every emotional burden.
    • Body care: gentle movement, regular meals, sleep routines, and moments of quiet support emotional regulation.
    • Joy: music, prayer, nature, art, cooking, humour, reading, dancing, or anything that helps you feel present rather than performed.

    Positive psychology can be useful here when it's applied gently. Resilience is not pretending you weren't hurt. Compassion is not excusing bad behaviour. Happiness, at first, may look like one peaceful afternoon, one honest conversation, or one day with less fear.

    Healthy boundaries also widen as you heal. At first, a boundary might be, “I won't answer that message.” Later it becomes, “I won't build my life around people who only value me when I abandon myself.”

    Navigating Complexities in the Indian Context

    Recovery can look different in India because relationships often sit inside wider systems. Family hierarchy, financial dependence, marriage pressure, respect for elders, and silence around mental health can all shape what is realistic.

    That matters. Many survivors aren't deciding between “leave” and “stay.” They're deciding how to survive in a setting where they may not be free to leave immediately.

    When the abuser is a parent or elder

    This is one of the most painful situations because cultural values can be used against the survivor. You may hear that loyalty means obedience, that gratitude means silence, or that seeking therapy is disrespectful.

    In India, 74% of families discourage mental health treatment for children due to stigma, and a 2025 study found 81% of adult survivors of parental narcissistic abuse felt unable to access professional help, highlighting the need for confidential online counselling and community support, as described in this discussion of stigma and access barriers in India.

    If that describes your situation, your first goal may be emotional distance rather than physical distance. That can include shorter conversations, fewer personal disclosures, neutral responses, and finding safe times for counselling outside the family's attention.

    When you cannot fully separate

    Some survivors are co-parenting. Some depend on shared housing. Some are managing legal, social, or financial constraints. Some are trying to keep family peace while protecting their own well-being.

    In these cases, use a layered approach:

    • Keep communication functional: stick to logistics, dates, tasks, and necessary decisions.
    • Reduce emotional hooks: don't argue about your motives, character, or memory.
    • Create support outside the home: a counsellor, one trusted friend, a support group, or confidential online counselling can become a lifeline.
    • Protect your routine: regular food, rest, work structure, prayer or mindfulness, and movement give the nervous system more stability.

    Honour culture without abandoning yourself

    Many survivors fear that healing means becoming cold, rebellious, or cut off from their roots. It doesn't have to.

    You can value family and still reject emotional harm. You can respect elders and still refuse cruelty. You can care about community and still seek therapy, counselling, and tools that support your mental health.

    The Indian context also makes privacy important. If in-person support feels difficult, confidential online counselling may be the safest first step. For many people, that privacy is what makes honesty possible.

    Your Path to Long-Term Resilience and Support

    Long-term recovery doesn't mean you never feel triggered again. It means triggers stop running your life. You learn what pulls you off balance, how your body signals danger, and what helps you return to steadiness.

    That is resilience in practice.

    What progress may look like

    You may notice that you pause before reacting. You may stop overexplaining. You may feel less drawn to chaos and more drawn to calm. Your relationships may become simpler, your work life may feel less consuming, and your sense of well-being may come back in small, believable pieces.

    A hopeful point from India-based data is that a study of 500 individuals in India found that with sustained therapy and self-care, survivors of narcissistic abuse can see drastic improvement in as little as six months to one year. The same report notes that early professional help is a statistically significant factor in shortening recovery duration, according to this India-focused recovery timeline overview.

    A person standing on a dirt path looking out at a scenic landscape during a bright sunset.

    How to protect your future peace

    A few habits make relapse into old patterns less likely:

    • Notice early red flags: contempt, boundary-pushing, chronic blame, intense charm followed by control, or pressure to ignore your own discomfort.
    • Track your state: when stress, anxiety, burnout, or low mood rise, ask what changed in your environment, routine, or relationships.
    • Stay connected to support: therapy or counselling can remain useful even after the crisis stage has passed.
    • Use tools wisely: journals, support groups, reflection exercises, and assessments can deepen self-understanding, but assessments are informational, not diagnostic.

    Recovery is less about becoming who you were before, and more about becoming someone who no longer abandons herself to stay connected.

    If you're looking for support, choose professionals who understand trauma, boundaries, family systems, and the overlap between emotional abuse, anxiety, depression, and chronic stress. The right support should help you feel clearer, safer, and more able to live according to your own values.

    You don't need to promise yourself a perfect future. You only need to keep taking the next honest step. That might be one counselling session, one boundary, one call to a trusted person, or one decision to believe your own experience.


    If you're ready to take that next step, DeTalks can help you find therapists, psychologists, and counsellors across India for concerns such as trauma, anxiety, depression, burnout, relationship pain, family conflict, and workplace stress. The platform also offers psychological assessments and screening tools that can support self-understanding, but these assessments are informational, not diagnostic. For many people, having one trusted place to explore therapy, counselling, and well-being support makes it easier to begin recovery with clarity and hope.

  • What Is Trauma Informed Care

    What Is Trauma Informed Care

    You might be here because getting help has felt harder than it should. Maybe you reached out for therapy or counselling for anxiety, depression, burnout, or workplace stress, and instead of feeling understood, you felt rushed, judged, or reduced to a list of symptoms.

    That experience can make anyone pull back. It can also create a painful question. If support itself feels unsafe, how are you supposed to heal?

    An Introduction to Compassionate Support

    A young professional in Bengaluru books a counselling session after months of poor sleep, constant worry, and rising workplace stress. In the first version of the story, the therapist quickly asks, “Why can't you cope better?” The client leaves feeling smaller than when they arrived.

    Now picture the same person in a different room. The therapist speaks gently, explains what the session will include, checks whether any topic feels too difficult for today, and says, “We can go at your pace.” That moment doesn't erase pain, but it changes the emotional climate completely.

    A distressed woman sitting at a desk while a professional in the background offers support during session.

    That difference is the heart of trauma informed care. It isn't only about treating trauma after a terrible event. It's about offering support in a way that helps people feel safe, respected, and in control, especially when life has already made them feel the opposite.

    What this means in everyday life

    Trauma can come from many places. In India, it may be linked to family violence, accidents, disasters, discrimination, medical experiences, workplace harassment, or ongoing pressure that wears a person down over time. Some people know exactly what affected them. Others only know that certain situations make their body tense, their mind race, or their trust disappear.

    A trauma-informed approach starts with that reality. It assumes that distress often has a story behind it, even if the story isn't fully spoken yet.

    Being trauma-informed means asking, “How can I make this interaction safer for you?” before asking someone to open up.

    India isn't only part of this conversation. It is helping lead it. India accounts for 11.4% of all trauma-informed care interventions implemented across 39 low- and middle-income countries, making it the single country with the most studies (n=29) in this field, reflecting a strong India-first foundation for TIC practices while remaining globally relatable, according to this review of interventions across low- and middle-income countries.

    If you want a practical companion piece focused on the therapy relationship itself, this guide to trauma-informed therapy can help you recognise what supportive care may look like in real sessions.

    Why people often feel confused by the term

    Many readers hear the phrase and think it must be a specialised treatment for severe trauma only. It's broader than that. Trauma-informed care is a way of relating. It shapes how a receptionist greets you, how a therapist asks questions, how a doctor explains a procedure, and how an organisation handles privacy, consent, and choice.

    That's why this topic matters not only for mental health professionals, but also for clients, families, HR leaders, teachers, and anyone trying to support another human being with care.

    The Shift From What's Wrong to What Happened

    The easiest way to understand what is trauma informed care is to think about medical gloves. A doctor doesn't wait for proof of infection before using gloves. Gloves are a standard precaution that protects everyone in the room.

    Trauma-informed care works in a similar way. It treats emotional safety as something that should be built into every interaction, not reserved only for people whose trauma history is already known.

    A change in the main question

    The old question is often, “What's wrong with you?” Even when people don't mean harm, that question can sound blaming. It suggests the person is the problem.

    The trauma-informed question is gentler and more accurate. “What happened to you?” That shift helps people understand anxiety, depression, anger, numbness, or shutdown as possible responses to difficult experiences rather than evidence of weakness.

    The lens can widen even further. Trauma-Informed Care operates as a universal precaution framework where the clinical focus moves from “What's wrong with you?” to “What happened to you?” and ultimately to “What's strong with you?”, as described by the University at Buffalo Institute on Trauma and Trauma-Informed Care.

    Practical rule: A trauma-informed provider doesn't rush to interpret behaviour before understanding context.

    How this feels for the person receiving care

    Take a college student in Pune who misses classes, feels panicky before presentations, and says, “I'm just lazy.” A non-trauma-informed response might focus only on discipline or performance. A trauma-informed response gets curious about what happens in the student's body, what situations trigger fear, and what support would make attendance feel possible.

    That same shift matters in hospitals, schools, and workplaces. If an employee becomes withdrawn after repeated public criticism from a manager, a trauma-informed supervisor won't begin with “Why are you so unprofessional?” A better starting point is to ask what conditions would help the employee feel safer, clearer, and more able to function.

    What trauma informed care is and isn't

    Trauma-informed care is not one single therapy method. It's not a script. It's not a demand that people disclose painful memories.

    It is a framework for contact. It shapes tone, pace, language, boundaries, and decision-making. A person can receive trauma-informed support in counselling, general healthcare, social work, education, and even routine administrative interactions.

    That's why the idea is so powerful. It doesn't depend on dramatic disclosures. It depends on everyday respect.

    The Six Core Principles of Trauma Informed Care

    The most practical way to recognise trauma informed care is to look for its six core principles. These principles come from SAMHSA and act like design rules for how support should feel and function.

    A diagram illustrating the six core principles of trauma-informed care including safety, transparency, support, and cultural considerations.

    The TIC approach is anchored in six key principles that serve as technical benchmarks for organisational design: Safety, Trustworthiness and Transparency, Peer Support, Collaboration and Mutuality, Autonomy/Voice/Choice, and Cultural/Historical/Gender considerations, according to SAMHSA's trauma-informed approaches guidance.

    Safety

    Safety includes both physical and emotional safety. A person should feel that the room, the process, and the relationship are not going to overwhelm or humiliate them.

    In an Indian clinic, this might mean a quiet waiting area, a clear explanation before sensitive questions, or a counsellor checking whether the door should stay slightly open or closed. Safety also means not forcing disclosure before trust exists.

    Trustworthiness and transparency

    People tend to relax when they know what's happening and why. Uncertainty can feel threatening, especially for someone who has lived through chaos, control, or betrayal.

    A trauma-informed therapist might say, “First I'll ask a few background questions, then we'll decide together what feels most useful today.” That simple clarity can reduce anxiety and help the person stay engaged.

    To make the framework easier to remember, this short visual overview can help:

    Peer support

    Healing often becomes easier when people don't feel alone. Peer support means learning from others who understand, whether through support groups, shared recovery spaces, or community-based programmes.

    A woman coping with postnatal distress in Chennai may feel less ashamed when she meets others who have also struggled. Shared experience can lower isolation in a way professional expertise alone sometimes can't.

    Sometimes the most regulating sentence in the room is, “You're not the only one who has felt this.”

    Collaboration and mutuality

    Trauma often involves powerlessness. So a trauma-informed relationship tries to reduce unnecessary power differences.

    This can be as simple as a therapist asking, “Would you prefer to start with what's been happening this week, or would you like me to guide us?” In hospitals and counselling centres, it also means staff treat people as participants in care, not passive recipients.

    Empowerment, voice, and choice

    This principle brings the person's agency back into the room. They get choices about pace, goals, boundaries, and what support feels manageable.

    For example, if a client becomes tearful while discussing family pressure around marriage, the therapist might offer options. Pause. Continue. Shift to grounding. Come back next session. Choice itself can be healing.

    Cultural, historical, and gender issues

    Care isn't trauma-informed if it ignores identity and context. In India, family roles, gender expectations, caste realities, religion, language, migration, and community reputation can shape how suffering is experienced and expressed.

    A counsellor who understands that a client's distress is tied not only to private emotions but also to family duty, social stigma, or discrimination is more likely to offer care that feels respectful and relevant. This principle asks providers to stay aware of bias and to adapt support to real lives, not idealised ones.

    Trauma Informed Care Versus Trauma Therapy

    Many people use these terms as if they mean the same thing. They don't. That confusion can lead to mismatched expectations.

    Trauma-informed care is the environment and approach. Trauma-specific therapy is the clinical treatment used when someone wants help processing traumatic experiences more directly.

    Trauma Informed Care vs Trauma Therapy At a Glance

    Aspect Trauma-Informed Care (TIC) Trauma-Specific Therapy
    Primary focus Making services feel safe, respectful, and non-triggering Helping a person process and heal trauma more directly
    Scope Broad and universal. It can apply to all clients and settings Targeted. It is used when a clinician and client decide it fits the person's needs
    Who provides it Ideally all staff, including therapists, doctors, reception staff, teachers, and support teams Trained mental health clinicians
    Main question “How do we provide care in a safe and collaborative way?” “How do we treat trauma-related distress in this person's life?”
    What it includes Consent, transparency, emotional safety, choice, respectful communication Structured therapeutic methods, guided processing, and deeper clinical work
    Is disclosure required No. A person doesn't have to describe trauma for care to be trauma-informed Sometimes trauma history becomes part of treatment, but only within a safe clinical process
    Where you may see it Hospitals, counselling centres, schools, NGOs, workplaces, community programmes Private practice, specialised clinics, hospital mental health services

    Why this difference matters

    A person may benefit from trauma-informed support even if they never enter trauma-focused therapy. For example, someone dealing with anxiety, workplace stress, or relationship strain may need a therapist who works slowly, explains clearly, and respects boundaries.

    Another person may want both. They may first need a safe, stable counselling relationship and later choose a more focused trauma therapy process with a trained clinician. If you want to see how one provider describes that more targeted form of care, this overview of Trauma Therapy Ohio offers a useful example of trauma-specific treatment language.

    A simple way to remember it

    Think of TIC as the soil and trauma therapy as the treatment plan. Good soil doesn't replace treatment. But without safe soil, growth is harder.

    That's why the distinction matters so much for well-being. One shapes the conditions. The other shapes the intervention.

    What Trauma Informed Support Looks Like in Practice

    A precise definition isn't always the top priority. Instead, individuals often need to understand what to look for when choosing a therapist, clinic, or counselling service.

    A trauma-informed provider often reveals themselves in small moments. They don't push for details before trust exists. They explain what they're doing. They notice signs of overwhelm and adjust rather than insisting a person continue.

    Signs you can observe early

    You can often spot trauma-informed support before the first full session. Look at the provider's language, intake process, and response to your comfort.

    • Respectful wording: Their website or profile uses language that feels human, not shaming. It speaks about support, resilience, and well-being rather than blaming people for struggling.
    • Clear expectations: They explain confidentiality, session structure, and fees in plain language so you're not left guessing.
    • Choice in the process: They ask whether there's anything that would help you feel more comfortable during therapy or counselling.
    • Pace and consent: They don't assume you must talk about painful events immediately.
    • Attention to the body: They recognise that stress, anxiety, or depression may show up physically through sleep problems, restlessness, headaches, or shutdown.
    • Collaboration: They ask what you want from support rather than deciding everything for you.

    Questions you can ask a provider

    You don't need special training to ask good questions. You just need permission to be curious.

    • About safety: “How do you help clients feel safe if difficult feelings come up?”
    • About pace: “If I'm not ready to discuss certain experiences, is that okay?”
    • About collaboration: “How do you involve clients in decisions about goals and treatment?”
    • About culture: “How do you take family, culture, or identity into account in your work?”
    • About stress reactions: “How do you work with anxiety, burnout, or workplace stress when trauma may be part of the picture?”

    A good provider won't be offended by these questions. They'll usually welcome them.

    Why these practices matter

    Trauma-informed care isn't just a nice tone. It has been linked with meaningful improvements. Implementation of TIC principles has demonstrated significantly higher prenatal appointment attendance rates (p<.001) and a 44% decrease in depressive disorder when adverse childhood experiences are prevented, as reported in this review of trauma-informed care in healthcare settings.

    Those findings matter because engagement is often the first hurdle. People stay with care when care feels survivable. They return when they feel respected.

    Practical barriers matter too. In many settings, people also need clarity around logistics such as paperwork and payment. For professionals building trauma-sensitive services, operational details like mental health billing and reimbursement can affect whether support remains accessible and organised without adding more stress for clients.

    One important clarification

    Assessments and screening tools can be useful when you're trying to understand your symptoms, patterns, or stress load. But they are informational, not diagnostic. They can guide questions and next steps, yet they don't replace a thoughtful clinical evaluation by a qualified professional.

    That distinction protects people from two common mistakes. One is dismissing their pain because a tool doesn't capture it fully. The other is assuming a score tells the whole story.

    Implementing Trauma Informed Care in India

    In India, trauma-informed care has to do more than import a global model. It has to listen to local realities. That includes family systems, language diversity, social hierarchy, rural and urban differences, migration, gendered pressure, and the long aftereffects of discrimination.

    This matters for both patients and providers. A clinician may want to offer excellent therapy, but if the organisation rushes intake, ignores staff burnout, or uses rigid policies, the care can still feel unsafe.

    A five-step infographic detailing the process for implementing trauma-informed care within the Indian healthcare landscape.

    Where India has strength and where it still needs work

    India has a meaningful base of trauma-informed practice and scholarship, as noted earlier. That's encouraging because it means this conversation isn't foreign to the Indian context.

    At the same time, important gaps remain. A critical gap exists as no major Indian national mental health policy (until 2025) explicitly integrates caste or colonial trauma into TIC frameworks, despite 68% of respondents in a survey reporting lifetime discrimination-related distress, according to the American Academy of Pediatrics page on trauma-informed care.

    That gap has real consequences. If care talks about trauma in general terms but avoids caste-based humiliation, historical oppression, or chronic discrimination, many clients won't feel fully seen. The language may sound kind, but the experience may still feel incomplete.

    What implementation can look like on the ground

    Organisations don't become trauma-informed by adding the phrase to a brochure. They build it through repeated choices.

    • Train the whole team: Reception staff, nurses, counsellors, doctors, managers, and HR teams all shape the client experience.
    • Create feedback loops: Ask clients what felt supportive, what felt difficult, and what could be changed.
    • Support the providers: People who care for others also need supervision, rest, and emotional support so burnout doesn't harden their responses.
    • Adapt to local communities: Urban private practice, a district hospital, a school counsellor, and a community NGO won't all use the same model.
    • Review policies, not only people: Appointment systems, privacy procedures, waiting room design, and complaint handling all matter.

    Care becomes trauma-informed when organisations make safety visible in systems, not only in slogans.

    The provider's experience matters too

    Many clinicians in India are carrying heavy caseloads and emotional strain. Some are hearing stories of violence, loss, neglect, and despair every day. Without support, even skilled professionals can become numb, reactive, or exhausted.

    A trauma-informed system recognises this openly. Provider well-being isn't a luxury. It protects compassion, steadiness, and the ability to stay present with another person's pain.

    This is also where positive psychology has a place. Trauma-informed work isn't only about reducing harm. It's about building resilience, restoring dignity, strengthening connection, and helping people experience more safety, meaning, and moments of happiness in ordinary life.

    Finding Your Path to Trauma Informed Support

    If you've had a painful experience with help in the past, it makes sense to feel cautious. Caution isn't failure. It's often a sign that your mind and body are trying to protect you.

    The good news is that support can feel different. Good therapy and counselling don't have to rely on pressure, shame, or forced disclosure. They can be grounded in choice, collaboration, and respect.

    What to remember as you look for help

    Start with the basics. Read provider bios carefully. Look for phrases such as trauma-informed, client-led, collaborative, culturally responsive, strengths-based, or person-centred.

    Then trust your early impressions. If a provider welcomes your questions, explains their process clearly, and treats your comfort as part of the work, that's often a healthy sign. If you feel dismissed or pushed too quickly, it's okay to keep looking.

    Use tools as support, not labels

    Self-assessments can help you organise your thoughts before reaching out. They can highlight concerns around anxiety, depression, burnout, resilience, or relationship stress and make it easier to describe what you've been feeling.

    Just keep one thing in mind. Assessments are informational, not diagnostic. They're best used as starting points for reflection and conversation, not as final answers about who you are or what you need.

    A trauma-informed path doesn't promise instant relief. It offers something steadier. A better chance of feeling safe enough to heal, supported enough to grow, and respected enough to stay connected to your own voice.


    If you're ready to look for support with more clarity and choice, DeTalks can help you explore therapists, read how professionals describe their approach, and use assessments as informational tools to better understand your needs before starting counselling. It's a practical way to find care that supports well-being, resilience, and a more confident next step.

